Patient Care is the smallest section of the ARRT® Radiography exam, which many students simply call the registry. It still has the largest single scoring category, and these are facts you will use with real patients. This guide covers what the outline lists, with the source for each high-stakes fact.
This page is a study reference, not clinical guidance. Follow your training, your facility’s protocols and the licensed clinicians you work with.
How many Patient Care questions are on the ARRT exam?
Patient Care has 33 of 200 scored questions through February 28, 2027, and 31 from March 1, 2027. That is about 1 in 6 today. The exam adds 30 unscored pilot questions.
Patient Care -2
Safety -4
Image Production same
Procedures +6
Each exam has 200 scored questions. Source: ARRT Radiography Content Specifications 2022 and 2027.
Patient Care has one category, Patient Interactions and Management. The other sections split into two or three categories, which is why this one is the largest of the eight, even though the section is the smallest of the four. For the full exam plan, read how to pass the ARRT Radiography exam.
ARRT doesn’t publish how many questions cover each topic, so any claim that a fact is “the most tested” is a guess.
What does the Patient Care section cover?
Both outlines use seven headings:
- Ethical and legal aspects: consent, HIPAA, the AHA Patient Care Partnership, verification, legal terms and doctrines, restraints, and the ARRT Standards of Ethics.
- Interpersonal communication: modes, barriers, explaining medical terms and patient education.
- Physical assistance and monitoring: body mechanics, transfers, tubes and lines, oxygen delivery, vital signs and fall prevention. The 2022 outline calls this “Ergonomics and Monitoring”.
- Medical emergencies: latex and other non-contrast allergic reactions, cardiac or respiratory arrest, trauma, seizures and diabetic reactions.
- Infection control: the chain of infection, asepsis, Standard Precautions, transmission-based precautions and neutropenic precautions.
- Toxic or hazardous material: chemicals, chemotherapy and the safety data sheet.
- Pharmacology: patient history, venipuncture, contrast types, lab values such as eGFR, and reactions.
What changes in Patient Care on March 1, 2027?
The section drops from 33 questions to 31. The 2027 outline also adds these items:
- Exam coding, under verification.
- Need for a medical interpreter, under pre- and post-exam instructions.
- Patient scheduling, under patient education.
- Patient comfort and modesty, under monitoring.
- Communication of critical findings to the health care team, under emergencies.
- IV supplies under disposal, and disinfectants under hazardous materials.
Not sure which section is weakest? Try the free practice test.
How do you confirm a patient’s identity?
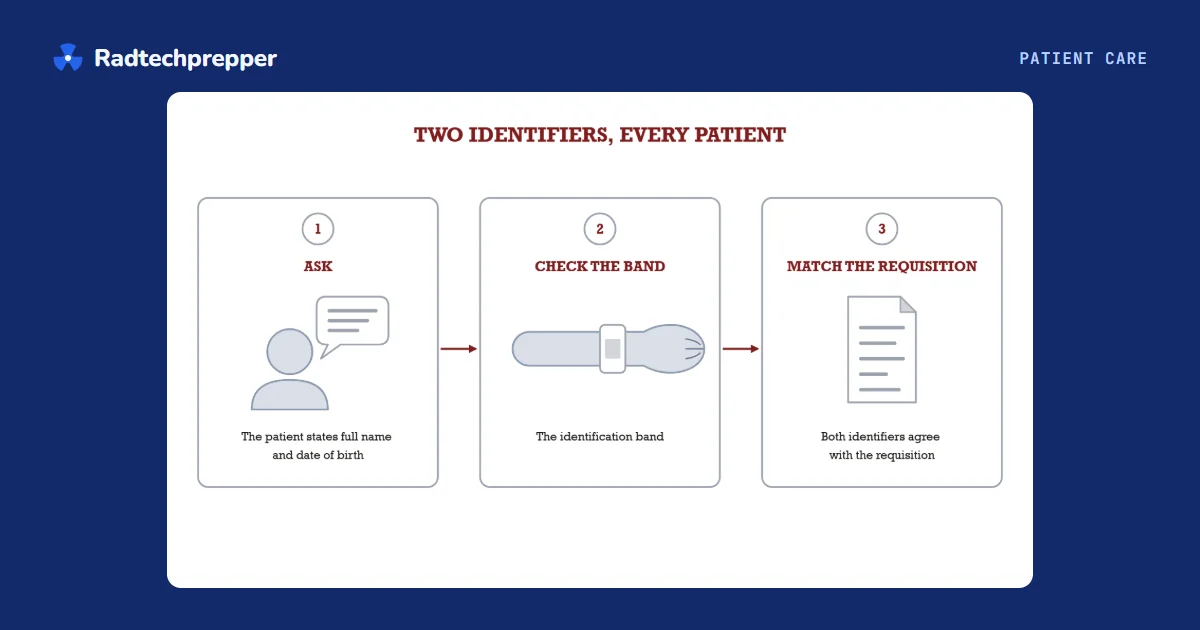
Use at least two identifiers before you do anything to the patient. Name and date of birth are the usual pair. WHO’s patient identification guidance says neither identifier should be the room number.
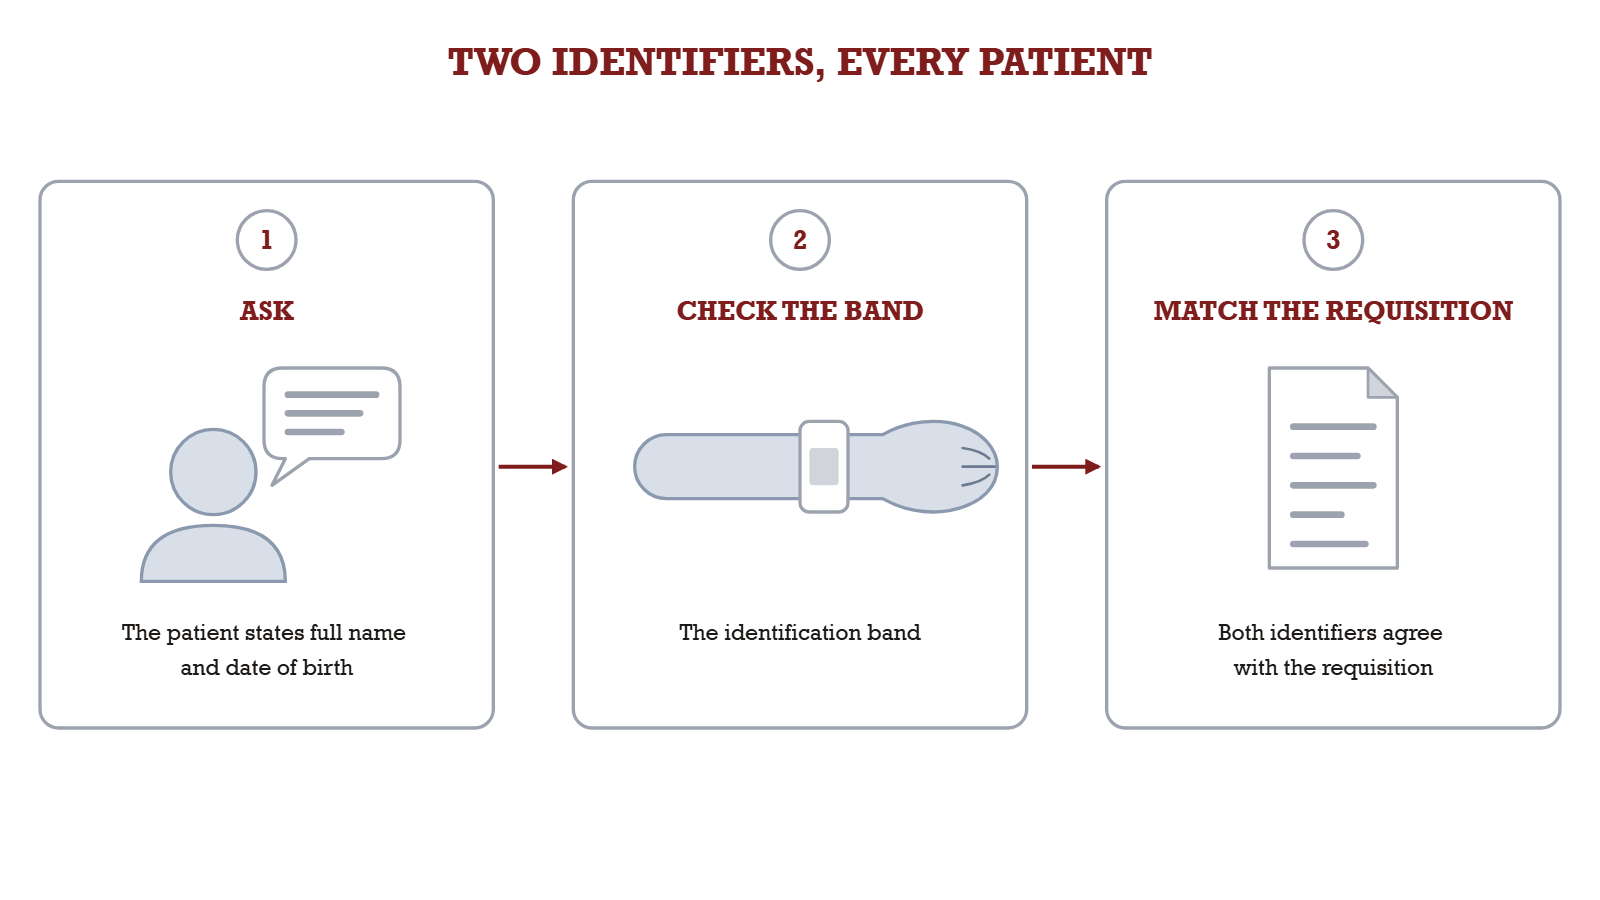
Verification also covers comparing the order to the clinical indication. Both outlines list it beside patient identification.
Which vital signs should you memorize?
The pulse, breathing, temperature, fever and oxygen saturation numbers match Ehrlich and Coakes’s patient care textbook. The blood pressure categories come from NHLBI, and the systolic hypotension line comes from the ACR contrast manual.
| Vital sign | Adult normal | Words to know |
|---|---|---|
| Pulse | 60 to 100 beats/min | Under 60 is bradycardia. Over 100 is tachycardia. |
| Respiration | 12 to 20 breaths/min | Under 12 is bradypnea. Over 20 is tachypnea. |
| Blood pressure | Under 120 and under 80 mm Hg | High from 130 systolic or 80 diastolic. Systolic under 90 is hypotension. Over 180 systolic or over 120 diastolic is a crisis. |
| Temperature | 98.6°F (37°C) oral average | Fever is 100.4°F or higher by mouth. |
| Oxygen saturation | 95% to 100% | Below 95% may mean tissues aren’t getting enough oxygen. |
Ehrlich and Coakes (2021) still calls 120 to 139 prehypertension and starts stage 1 at 140/90. NHLBI now uses 140/90 for stage 2, so go with NHLBI, and know your program’s table.
Oxygen saturation varies by source too. Ehrlich and Coakes prints 95% to 100% as normal on one page and treats anything under 90% as a concern on another. AARC’s 2022 guideline targets 94% to 98% for most hospitalized adults. Use the figure your question or program gives.
Children run differently. Ehrlich and Coakes lists a pulse of 125 beats/min for a term newborn and 120 at 6 months and 1 year, with much faster breathing than an adult’s. Don’t apply the adult ranges to a child. Our vital signs by age page has the full table, and the patient monitoring chapter covers how to take each one.
Which precautions go with which infection?
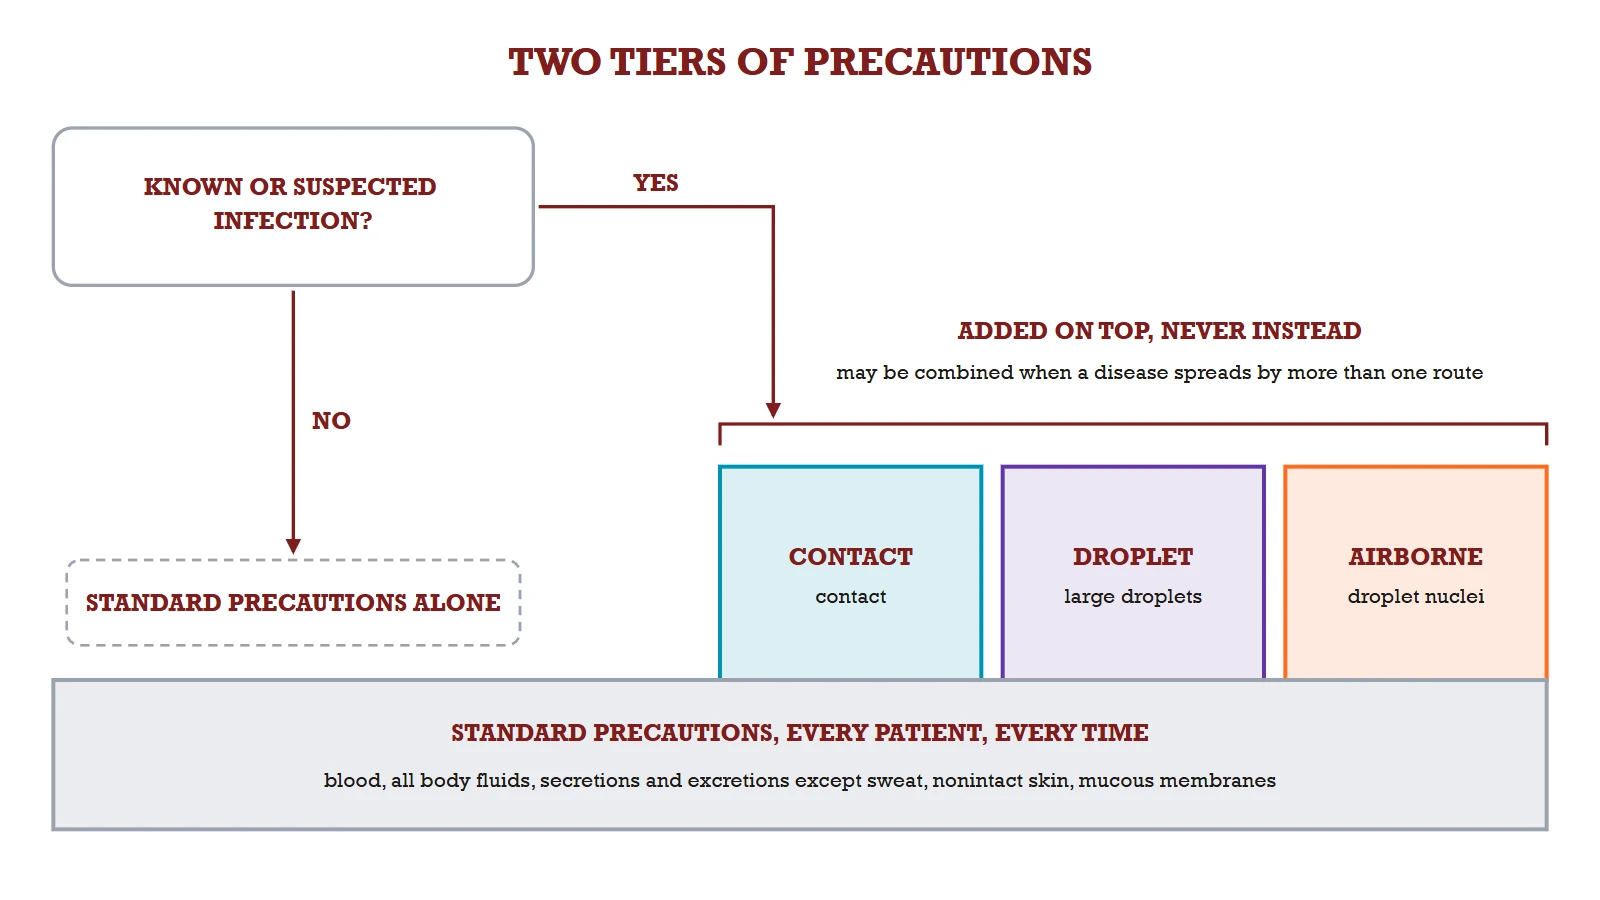
Standard Precautions apply to every patient. Treat blood, body fluids, secretions, excretions except sweat, non-intact skin and mucous membranes as potentially infectious. CDC notes that hand hygiene has often been cited as the single most important practice to reduce transmission.
Transmission-based precautions go on top of Standard Precautions, for known or suspected infections. They never replace them.
| Precaution | Examples in CDC’s Appendix A | What you wear |
|---|---|---|
| Contact | C. difficile, scabies, RSV in infants, young children and immunocompromised adults, and MRSA or VRE when the infection control program calls for it | Gloves on entry. A gown on entry when your clothes will touch the patient or nearby surfaces. |
| Droplet | Influenza, pertussis, mumps, rubella | A mask on entry to the room. |
| Airborne | Pulmonary or laryngeal TB, measles, chickenpox, disseminated zoster | A fit-tested N95 or higher for infectious TB. For measles, a respirator at least as protective as a fit-tested N95 on entry, even with evidence of immunity. For chickenpox and disseminated zoster, CDC’s isolation guideline makes no recommendation on mask or respirator type. Ehrlich and Coakes says anyone susceptible who must enter wears an N95 or higher. Follow your facility’s policy. A negative-pressure airborne isolation room with the door closed. |
Five details catch people out:
- RSV is Contact, not Droplet. CDC adds a mask according to Standard Precautions.
- Measles means a respirator, even if you’re immune. CDC says healthcare personnel entering the room wear at least N95-level protection, whatever their evidence of immunity. Staff without that evidence should stay out if immune staff are available.
- Chickenpox and disseminated zoster are Airborne plus Contact. Staff who aren’t immune should stay out of the room if immune staff are available. If they must enter, Ehrlich and Coakes says to wear an N95 or higher.
- The 3-foot droplet rule is older than the advice. CDC calls 3 feet an example of “a short distance”, not the only test, and tells you to mask on entry. Ehrlich and Coakes speaks of close contact, so go with CDC. CDC has no routine recommendation for eye protection on top of the mask for Droplet Precautions.
- C. difficile means soap and water. CDC recommends washing with soap and water whenever contact with spores is likely, and prefers it for C. difficile because alcohol rub has no sporicidal activity. Ehrlich and Coakes agrees, and says to clean shared equipment with bleach wipes. CDC adds that hypochlorite solutions may be required for cleaning if transmission continues.
Transport has its own rules. A Droplet or Airborne patient wears a mask outside the room, and CDC specifies a surgical mask, if possible, for Airborne. On Contact Precautions, cover the infected area, then put on clean PPE at the destination. Use patient-dedicated or disposable equipment where you can, and disinfect anything shared before the next patient.
So for a portable chest on a patient with active pulmonary TB, wear a fit-tested N95. A surgical mask alone isn’t the answer. Ehrlich and Coakes also describes the two-person method for isolation exams: a “dirty” radiographer positions the patient, and a “clean” one touches only the x-ray machine and the uncovered receptor. The infection control chapter covers the chain of infection and asepsis.
How are contrast reactions classified?
The ACR Manual on Contrast Media sorts acute reactions by severity and by type. Allergic-like reactions look like allergies. Physiologic reactions are a body response to the contrast. The type matters because a prior allergic-like reaction may call for premedication next time, and a prior physiologic reaction doesn’t.
| Severity | Allergic-like examples | Physiologic examples | What usually happens |
|---|---|---|---|
| Mild | Limited hives or itching, scratchy throat, nasal congestion, sneezing | Limited nausea, brief warmth or flushing, altered taste, headache, vasovagal reaction that resolves on its own | Self-limited. Many resolve with observation and no treatment. |
| Moderate | Diffuse hives, facial edema without shortness of breath, throat tightness without shortness of breath, wheezing with mild or no hypoxia | Protracted vomiting, isolated chest pain, hypertensive urgency, vasovagal reaction that responds to treatment | More pronounced, commonly needs medical management, and can become severe. |
| Severe | Facial edema with shortness of breath, laryngeal edema with stridor or hypoxia, wheezing with significant hypoxia, anaphylactic shock | Arrhythmia, seizures, hypertensive emergency, vasovagal reaction resistant to treatment | Often life-threatening. Call the emergency team. |
Ehrlich and Coakes says most patients feel warmth during the injection, and a metallic taste can occur, so warn the patient first. Warmth with itching palms and soles, trouble swallowing or a tight throat is different. The same book lists those as early signs of anaphylaxis, so call for help.
Your part: notify the radiologist or nurse, stay with the patient, watch the vital signs, have oxygen and the emergency cart ready, and document. For anaphylaxis, Ehrlich and Coakes says to alert the radiologist and call a code. Separately, if the patient reports pain or swelling at the injection site, ACR says to discontinue the injection. Drug decisions belong to the physician, but the outline lists emergency medications, so know them.
What treatment facts does the ACR list?
- Epinephrine, adult: 0.3 mg IM (0.3 mL of 1 mg/mL). It can repeat every 5 to 15 minutes up to 1 mg total. IV is preferred in a hypotensive patient.
- Epinephrine, child: 0.01 mg/kg IM, maximum 0.3 mg. By auto-injector, 0.15 mg under 30 kg and 0.3 mg at 30 kg or more.
- Hives: often no treatment. Diphenhydramine is an option if symptomatic.
- Oxygen by mask: 6 to 10 L/min, listed throughout the tables.
- Low blood pressure: raise the legs at least 60 degrees and give IV fluids. Ehrlich and Coakes prints feet up about 20 degrees and head up about 10 for a vasovagal reaction. Go with ACR, the current guideline. A slow pulse points to a vasovagal reaction, where the drug is atropine if severe. A fast pulse points to an anaphylactoid reaction, where the drug is epinephrine if hypotension persists.
Who is at higher risk of a contrast reaction?
- A prior allergic-like or unknown-type reaction to the same class of contrast. This is the greatest risk factor, at about 5 times the risk.
- Unrelated allergies. About 2 to 3 times the risk.
- Asthma. A modest increase, and these patients may be more prone to bronchospasm.
Allergic-like reactions to iodinated contrast are uncommon: about 0.6% overall and 0.04% severe. ACR doesn’t recommend restricting contrast or premedicating on the basis of asthma or unrelated allergies alone.
Shellfish is the classic trap. ACR says patients with shellfish or povidone-iodine allergies are at no greater risk than patients with other allergies.
Renal impairment is a separate issue. It raises concern for contrast-related kidney injury, not for an allergic-like reaction. Keep the two apart. Local effects such as extravasation and phlebitis, delayed reactions and metformin rules are in the contrast media chapter.
What oxygen flow goes with which device?
The physician orders the device and the rate. These ranges are from the AARC 2002 guideline for adults.
| Device | Flow | Oxygen delivered |
|---|---|---|
| Nasal cannula | Up to 6 L/min | 24% to 40% |
| Simple mask | 5 to 10 L/min, never below 5, to avoid rebreathing CO2 | 35% to 50% |
| Partial rebreathing mask | 6 to 10 L/min | 40% to 70% |
| Non-rebreathing mask | At least 10 L/min | 60% to 80% |
| Air-entrainment (Venturi) mask | Set by the adapter, so read its label | A preset percentage, accurate up to 40% |
Ehrlich and Coakes prints wider numbers, and so does our chapter: cannula 1 to 6 L/min at 24% to 45%, simple mask 40% to 60%, non-rebreather up to 100%, Venturi 24% to 60%. It also gives 1 to 10 L/min for face masks in general, without AARC’s floor of 5 for a simple mask. So don’t panic if a practice question uses a different range. The order of the devices stays the same.
High oxygen can harm a COPD patient who retains CO2. AARC’s 2022 guideline aims for an SpO2 of 88% to 92% in COPD, against 94% to 98% for most hospitalized adults. Ehrlich and Coakes explains this through the hypoxic drive, favors the Venturi mask, and limits nasal prongs to under 3 L/min. The ordered device and rate decide at the bedside.
What do you do in a medical emergency?
Call for help first in each of these. Then:
- Cardiac arrest: C-A-B, meaning compressions, airway, breathing. MedlinePlus, citing the 2025 AHA guidelines, gives 30 compressions and 2 breaths, 100 to 120 compressions a minute, about 2 inches (5 cm) deep, and an AED as soon as possible. It says to place the person on a firm, flat surface if possible, and Ehrlich and Coakes says the emergency cart has a board to slip under the patient. Ehrlich and Coakes says not to attempt CPR on a child or infant unless you’re certified for it.
- Fainting: lay the patient flat, raise the legs and check vital signs.
- Shock: stop the exam, lay the patient flat with the feet raised, get help, check blood pressure and be ready for CPR. If the patient is short of breath, raise the head and assist with oxygen. Ehrlich and Coakes gives this list, and elsewhere calls head-down Trendelenburg helpful in shock. The ACR hypotension table lists leg elevation and does not mention Trendelenburg.
- Seizure: prevent a fall, pad under the head and clear hazards, but don’t restrain the patient. Put nothing in the mouth. Note when it began, how long it lasted and which body parts it involved. Ehrlich and Coakes says to assist a patient who feels one coming to a supine position. ACR says to turn the patient on their side to avoid aspiration.
- Low blood sugar: if the patient can swallow safely, ACR lists oral glucose such as 15 g of tablets or gel, or half a cup of juice. If not, IV dextrose, or IM glucagon when there is no IV.
The patient monitoring chapter walks through each one in order.
How do you move a patient safely?
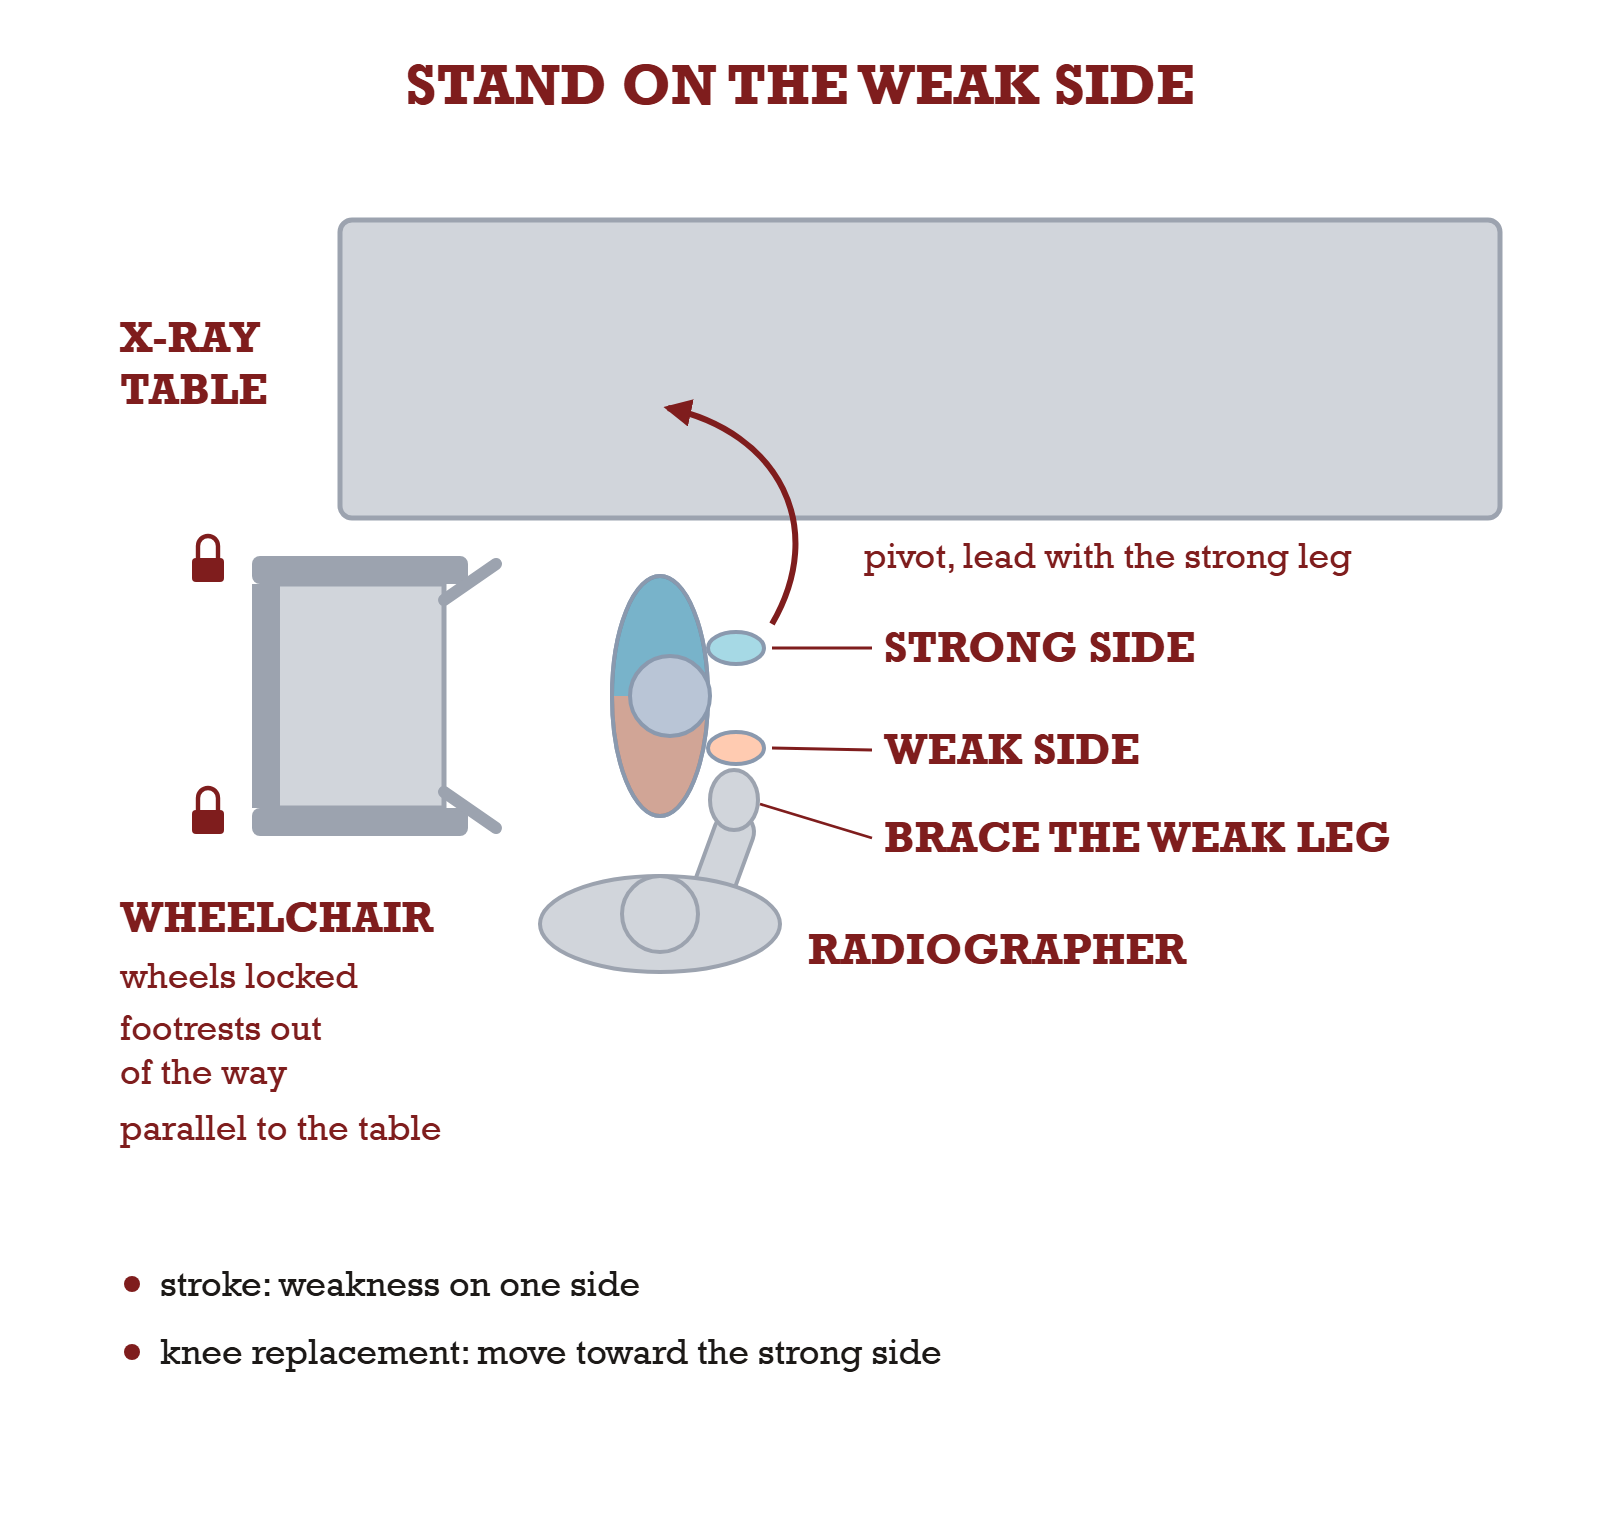
Keep the load close, use a broad base of support, and move your feet to turn rather than twisting your trunk. Lock the wheels before any transfer.
For a one-sided weakness, such as after a stroke, Ehrlich and Coakes says to stand on the weak side and brace the weak leg with your knee as the patient stands. Put the strong side next to the table and have the patient lead with the strong leg. The book adds that a stretcher is often the better choice for these patients.
The commonly taught way to choose an aid is to ask what the patient can still do:
| Device | Fits this patient |
|---|---|
| Gait belt (transfer belt) | Can stand but is weak or unsteady. It gives you a handhold, but the patient is still a fall risk. |
| Transfer board | Bridges a slide transfer, such as bed to chair or car to wheelchair. VA’s safe patient handling glossary says it’s often used for independent transfers and may be used for assisted ones. |
| Slider board or draw sheet | Lying down, moving between a stretcher and the table, with two or more staff. Not a substitute for a rigid spine board. |
| Hoyer (hydraulic) lift | In a wheelchair and can’t stand. Don’t use one until you’ve been trained. |
Books use “transfer board” and “slider board” loosely, so read the scenario. The transfer and support chapter covers these aids. Tubes and lines are in the patient monitoring chapter.
What makes consent valid?
Four conditions are commonly taught. Ehrlich and Coakes supports the first, second and fourth, and Torres states the third:
- The patient is of legal age, or a parent or guardian signs.
- The patient is of sound mind.
- Consent is given freely, with no coercion.
- The patient is adequately informed: the procedure, risks, benefits, alternatives and what happens if it isn’t done.
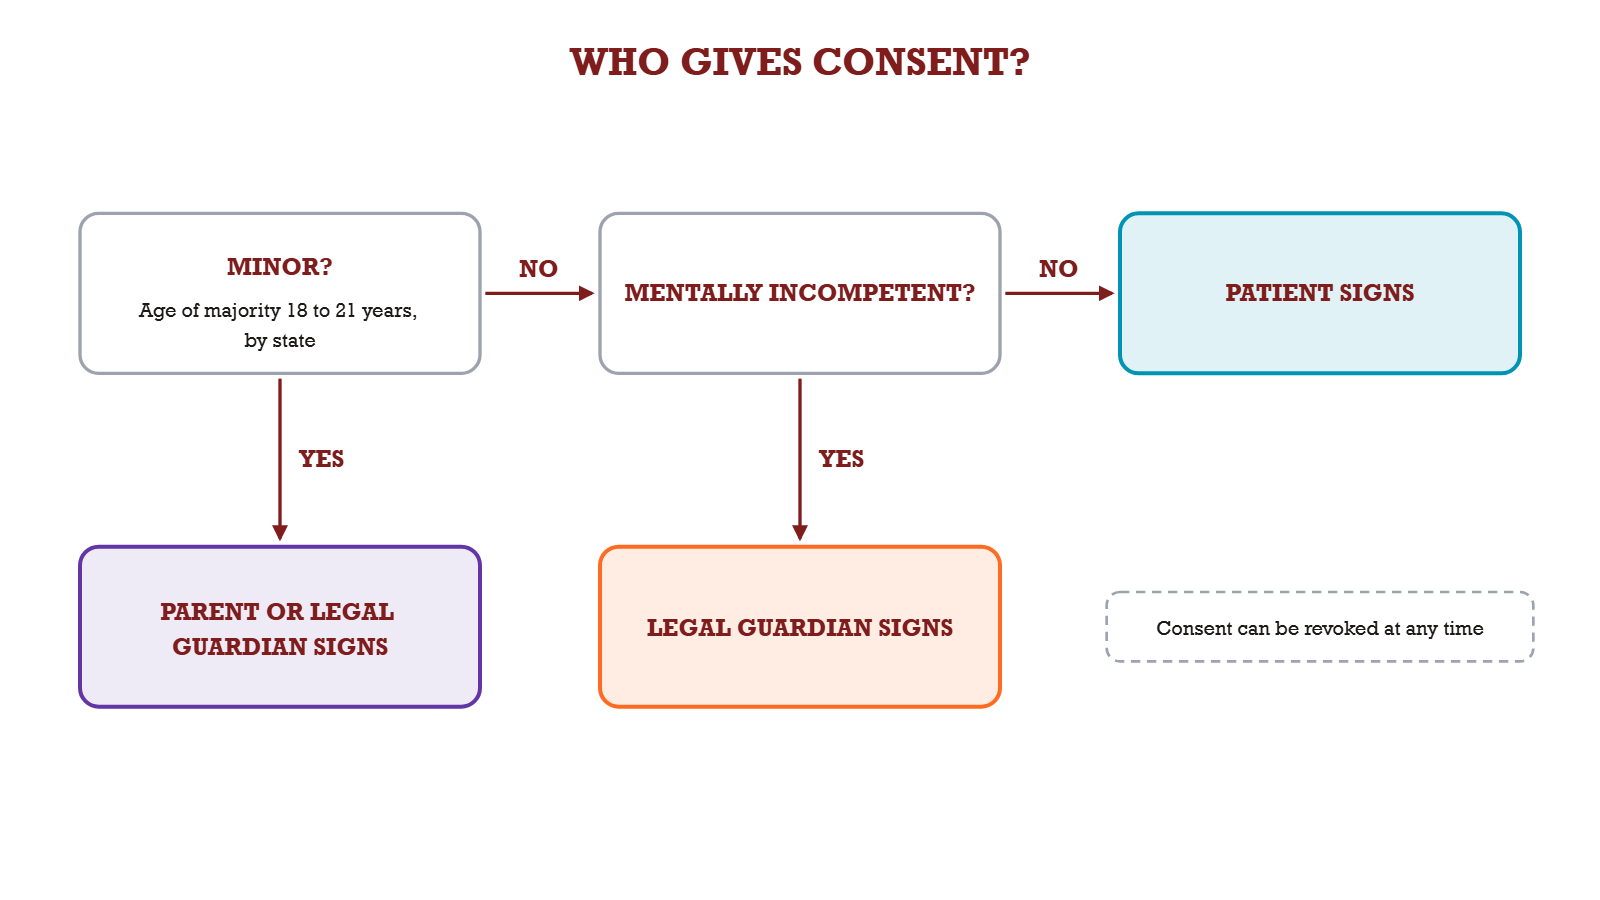
The outline names informed, oral and implied consent:
- Oral: consent given in spoken words. The outline names it, but the patient care books we read don’t define it or say when it’s enough, so follow your facility’s policy.
- Written informed: for anything with substantial risk or that is experimental. Ehrlich and Coakes names myelograms and arteriograms, and the form must be signed before sedation. Torres adds invasive procedures such as incisions and biopsies, and procedures that need sedation or anesthesia. Torres also lists “procedures that involve radiation”, which read literally would cover every x-ray. Ehrlich and Coakes treats routine exams as implied consent, as noted below, so follow your facility’s policy. The sources also differ on iodine contrast. For IV, intra-arterial or intrathecal iodine contrast, Ehrlich and Coakes says informed consent is usually required, because those routes clearly involve risk. ACR says IV contrast may be exempted because adverse events are uncommon, and that the decision rests on state law and institutional and departmental policy. Follow your facility’s policy at work, and the source your program names on a test.
- Implied: an emergency where nobody can give permission. Ehrlich and Coakes also uses “implied” for routine exams, through the patient’s continued acceptance of hospital care, so read the scenario.
What legal terms should you know?
These definitions follow Ehrlich and Coakes, in our words.
Intentional torts:
- Assault: a threat that creates fear of contact. No contact is needed.
- Battery: unconsented touching, such as doing the exam after the patient refused, or imaging the wrong patient. No prior threat is needed.
- False imprisonment: detaining a person against their will without justification. Inappropriate use of physical restraints may count.
- Defamation: maliciously spreading information that damages a reputation. Slander is usually spoken and libel is usually written. The book adds that a breach of confidentiality can give grounds for a slander suit.
- Invasion of privacy: disclosing confidential information without authority.
Negligence is the unintentional tort. A claim needs all four elements: a duty, a breach of that duty, an injury, and a link between the breach and the injury. Without an injury, there’s nothing to award.
Two doctrines are named in the outline. Res ipsa loquitur means “the thing speaks for itself”. Respondeat superior means “let the master respond”, so the employer is liable for employees’ negligent acts in the course of their work. That doesn’t shield you: under the rule of personal responsibility, you can be liable for your own negligence.
What do ARRT Rules 21 and 22 say?
Both are in the March 2026 Standards of Ethics, under “Duty to Report”.
- Rule 21: if you know of a violation or probable violation by a Registrant or Candidate, you must promptly report it in writing to ARRT.
- Rule 22: you must immediately tell your supervisor about an error in imaging, treating or caring for a patient. The duty applies whether or not the patient was injured.
Note the two different recipients: ARRT for Rule 21, your supervisor for Rule 22. That’s a good detail to drill, and the ethics, law and communication chapter has the wider set.
How should you communicate with different patients?
Explain what you’ll do, what they’ll feel and how long it takes. Then adjust to the patient: short sentences and a demonstration for a child or a confused patient, and more time for an older patient. Confirm understanding before the exposure.
For a patient with limited English, a qualified interpreter is the rule, and Ehrlich and Coakes calls for a medically trained one during consent. Federal rule 45 CFR 92.201 limits relying on an accompanying adult, and allows relying on a minor child only as a temporary measure in an emergency. The 2027 outline names the medical interpreter directly.
How should you study Patient Care?
Read the five chapters, then drill. This is our judgment on order, not an ARRT rule: start with infection control and contrast reactions, since the categories and severity tiers reward plain memorization. Then do law and ethics, which reward scenario practice.
If you’ve already sat the exam and this section let you down, the retake plan explains how to read your section scores. Your dose facts live next door, in the radiation protection guide.
The Patient Interactions practice set has 391 questions today and 389 from March 1, 2027. Every question has a written rationale.
The free tier is 3 chapters (Skull, Elbow and Shoulder, Urinary), 50 questions and a timed 200-question mock, with no card. Those are Procedures chapters, so no Patient Care chapter is free. You can still sign up free and test yourself on the mock. The five Patient Care chapters come with a paid plan: $39 a month, which renews until you cancel, $99 for a 90-day pass with no renewal, or $199 a year (about $16.58 a month), which renews yearly until you cancel. Paid plans open soon.