Below are 20 free practice questions for the ARRT® Radiography exam, with no signup. The answer sits directly after each question, so cover it with your thumb if you want to test yourself. Give yourself about 60 seconds per question. That matches the real exam: ARRT’s 2026 handbook lists 230 minutes of test time for 230 questions (200 scored plus 30 pilot).
These are not real registry questions, since ARRT exam content is confidential. We wrote them to test topics listed on ARRT’s content outlines. All 20 sit on both the 2022 outline and the 2027 outline, which starts March 1, 2027. A note follows any question the 2027 change touches.
They use ARRT’s most common format, multiple choice with one best answer. ARRT’s handbook says the exam also has select-multiple, sorting, image-selection and video-based items.
Twenty questions can’t match the exam’s weights, so treat this as a sample.
Patient Care: Patient Interactions and Management
This category has 33 scored questions now and 31 from March 1, 2027.
1. A patient arrives in the fluoroscopy room for an upper GI series. Before you do anything else with this patient, what comes first?
- A) Confirm the order with the radiologist
- B) Verify the patient’s identity using two identifiers
- C) Have the patient drink the barium suspension
- D) Position the patient on the fluoroscopy table
Answer: B. Identify the patient first, using at least two identifiers such as name and date of birth. Ehrlich and Coakes list this as a Joint Commission requirement. The room number never counts. (A) You do compare the order with the clinical indication, but you don’t need the radiologist for that on every exam, and a correct order on the wrong patient helps nobody. (C) and (D) come after you know who the patient is.
2. Five minutes after iodinated contrast, a patient has widespread hives, mild wheezing and vomiting that won’t stop. Blood pressure is stable and oxygen saturation is normal. This reaction is best categorized as:
- A) Mild: observe only
- B) Moderate: notify the radiologist or physician, keep the IV access and monitor
- C) Severe: call a code and prepare for immediate epinephrine
- D) Vasovagal: raise the legs and check vital signs
Answer: B. The ACR Manual on Contrast Media lists diffuse hives, bronchospasm with mild or no hypoxia, and protracted vomiting as moderate. These often need medical treatment and can worsen. (A) Mild means limited hives, limited vomiting or brief flushing. Ehrlich and Coakes treat nausea and vomiting as mild without that split, so if your book reads that way, the current ACR manual is the one to follow here. (C) Severe means problems such as laryngeal edema with stridor, bronchospasm with significant hypoxia, or anaphylactic shock. (D) A vasovagal reaction brings low blood pressure with a slow pulse, not hives or wheezing.
3. Under Rule 22 of the ARRT Standards of Ethics, when must you report an error made in caring for a patient?
- A) Only if the patient was injured
- B) Only if a supervisor specifically asks
- C) Immediately, whether or not the patient was injured
- D) Only if a colleague witnessed it
Answer: C. Rule 22 makes it a violation to fail to immediately report an error in imaging, treating or caring for a patient to your supervisor. The rule says the duty exists whether or not the patient suffered any injury. That rules out (A). (B) and (D) don’t appear in the rule: you report on your own, with or without a witness.
4. For a patient’s informed consent to be valid, the patient must:
- A) Have a witness present, be informed, be alert and be sober
- B) Be of legal age, be of sound mind, give consent freely and be adequately informed
- C) Have signed paperwork, have answered all screening questions, have medical insurance and be alert
- D) Have been told the cost, the duration and the alternatives, and have agreed
Answer: B. Option B is our short form of what the books require. Ehrlich and Coakes say the patient must be competent and must get a full explanation of the procedure, its risks and its benefits. Torres adds that consent must be freely given, without coercion. For a minor, Ehrlich and Coakes say only a parent or legal guardian may sign. For a mentally incompetent patient, only a legal guardian may sign. (A) A witness helps document consent, but doesn’t make it valid. (C) A signature counts only from someone with the legal capacity to give it, and insurance has nothing to do with it. (D) Leaves out age and capacity, and it lists cost, which isn’t a condition.
Image Production: Image Acquisition and Evaluation
This category has 26 scored questions now and from March 1, 2027. Receptor exposure is the outline’s term for what older books call density.
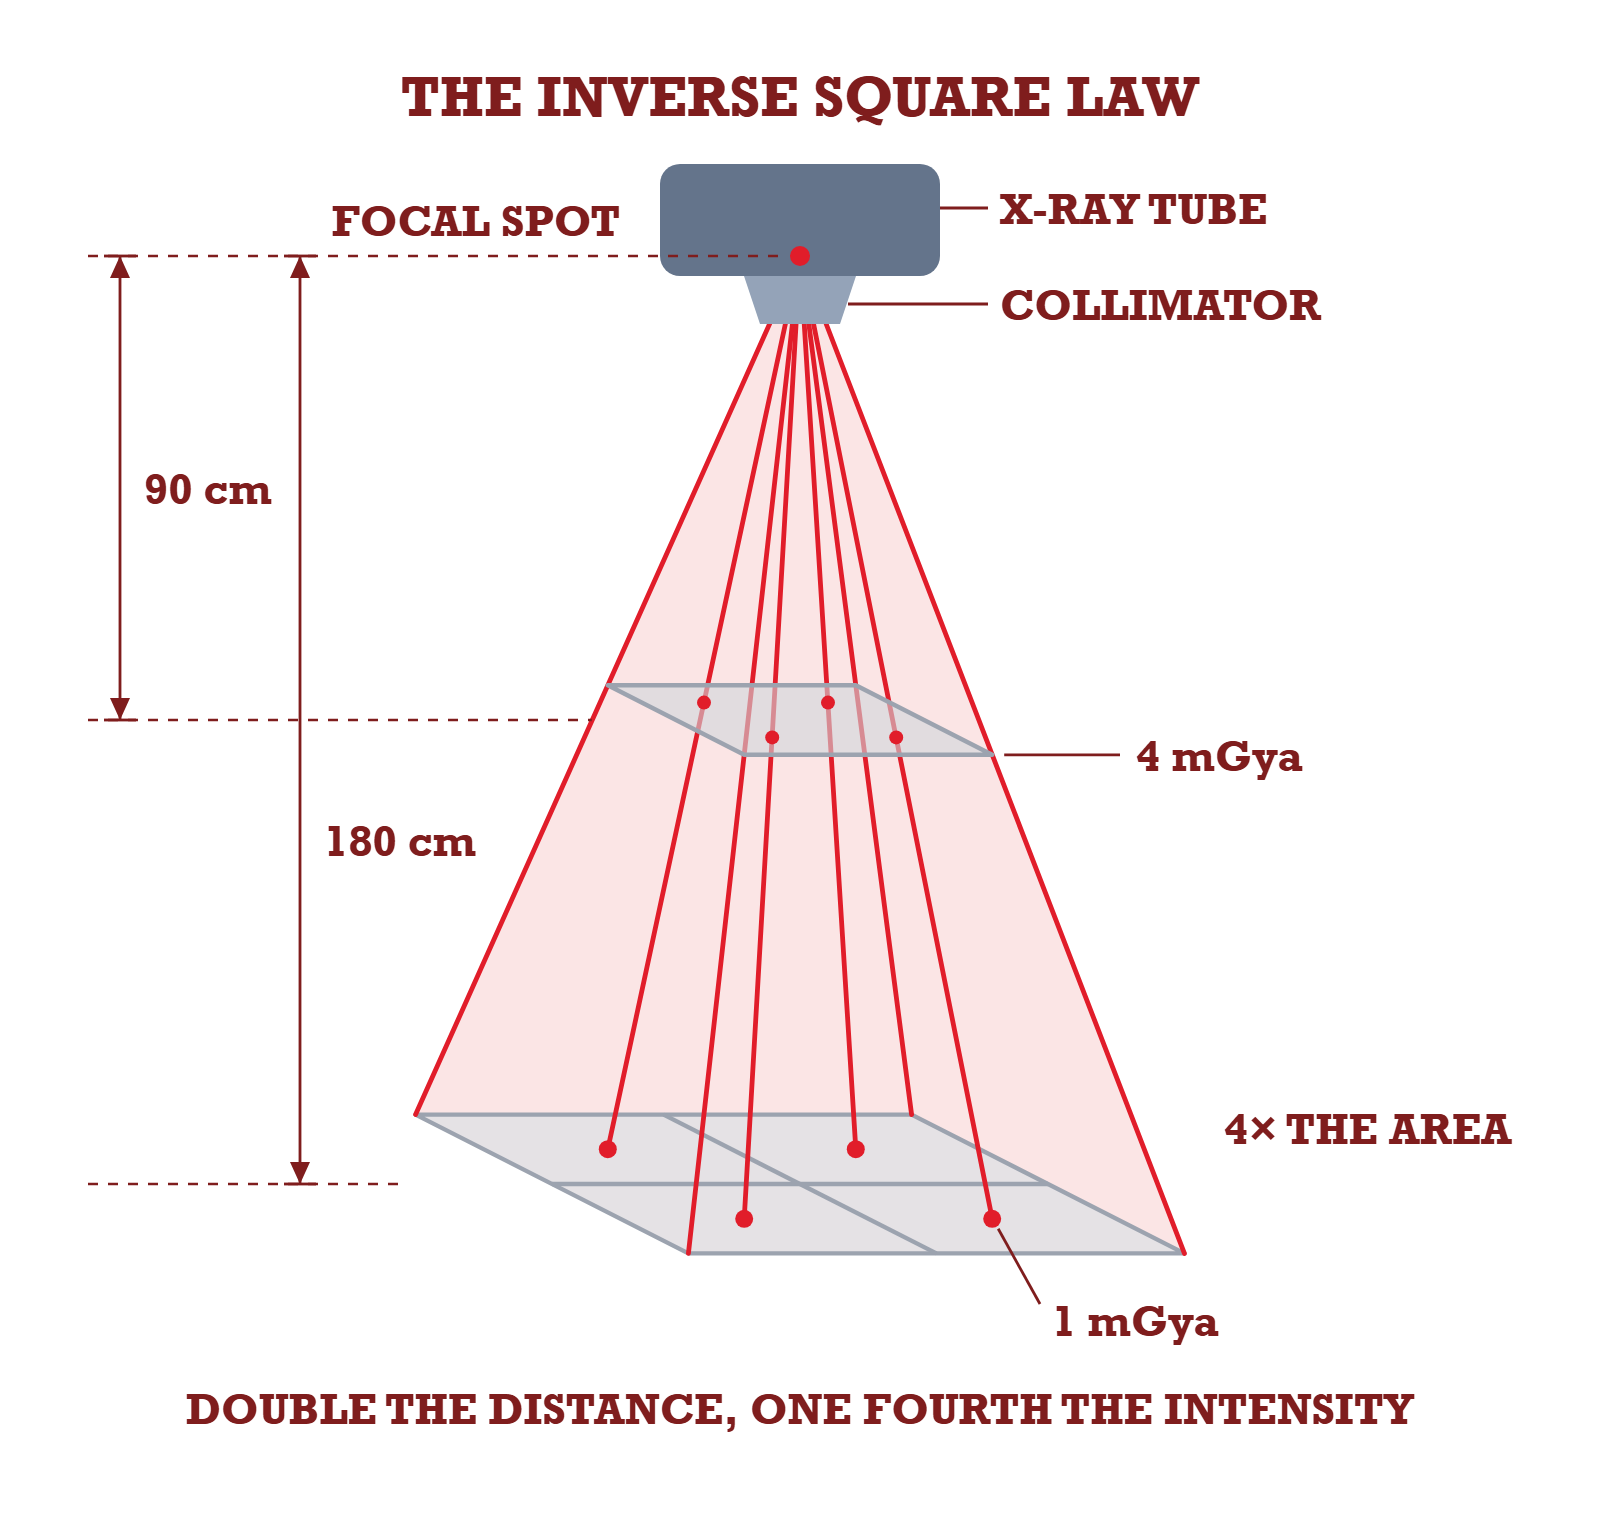
5. A technique of 80 kVp and 4 mAs at 72 inches (183 cm) SID gives the right receptor exposure. SID changes to 40 inches (102 cm), and nothing else changes. What new mAs keeps receptor exposure the same?
- A) 1 mAs
- B) 2 mAs
- C) 1.2 mAs
- D) 13 mAs
Answer: C. Use the exposure maintenance formula: new mAs = old mAs × (new SID ÷ old SID) squared. That gives 4 × (40 ÷ 72)² = 4 × 0.309, or about 1.2 mAs. A shorter distance means a more intense beam, so you need less mAs. (A) is about 20% too low. (B) forgets to square the ratio (4 × 40 ÷ 72 is about 2.2). (D) flips the ratio, which raises mAs when it should fall.
6. The exposure indicator shows a part received about twice the target receptor exposure. For the next exposure of this part, which single change returns receptor exposure to target without changing beam energy?
- A) Decrease mAs by 30%
- B) Decrease mAs by 50%
- C) Decrease kVp by 15%
- D) Decrease kVp by 5%
Answer: B. Receptor exposure is directly proportional to mAs, so half the mAs gives half the exposure, and mAs doesn’t change photon energy. (A) Too small: 30% is the old film-era figure for a just-visible change, and it won’t correct a doubled exposure. (C) The commonly taught 15% rule does about halve receptor exposure, but kVp changes beam energy, which the question rules out. (D) Also changes beam energy, and it is too small a change to correct this.
7. Using manual technique at the same kVp, you switch from a 5:1 grid to an 8:1 grid. To keep the same receptor exposure, you should:
- A) Halve the mAs
- B) Keep the same mAs
- C) Double the mAs
- D) Quadruple the mAs
Answer: C. The Average column of Bushong’s Bucky factor table lists 1 for no grid, 2 for 5:1, 4 for 8:1 and 5 for 12:1, and the table’s values shift with kVp. Going from 2 to 4 means twice the mAs. (A) and (B) would leave the receptor underexposed. (D) is the change from no grid to 8:1.
2027 note: grids stay on the outline, and the 2027 outline adds virtual grids.
8. The anode heel effect causes:
- A) Greater beam intensity on the cathode side of the field
- B) Greater beam intensity on the anode side of the field
- C) Heat to be retained at the anode bearings
- D) Light intensity to fall off at the edge of the light field
Answer: A. X-rays heading toward the anode side take a longer path through the target, so more are absorbed. That leaves the beam stronger on the cathode side, which is why you put thicker anatomy there. (B) reverses it. (C) and (D) describe other things: the heel effect is about x-ray intensity, not heat in the bearings or the collimator light.
2027 note: both outlines list the heel effect under factors affecting radiographic quality, so it sits here, not under Equipment Operation.
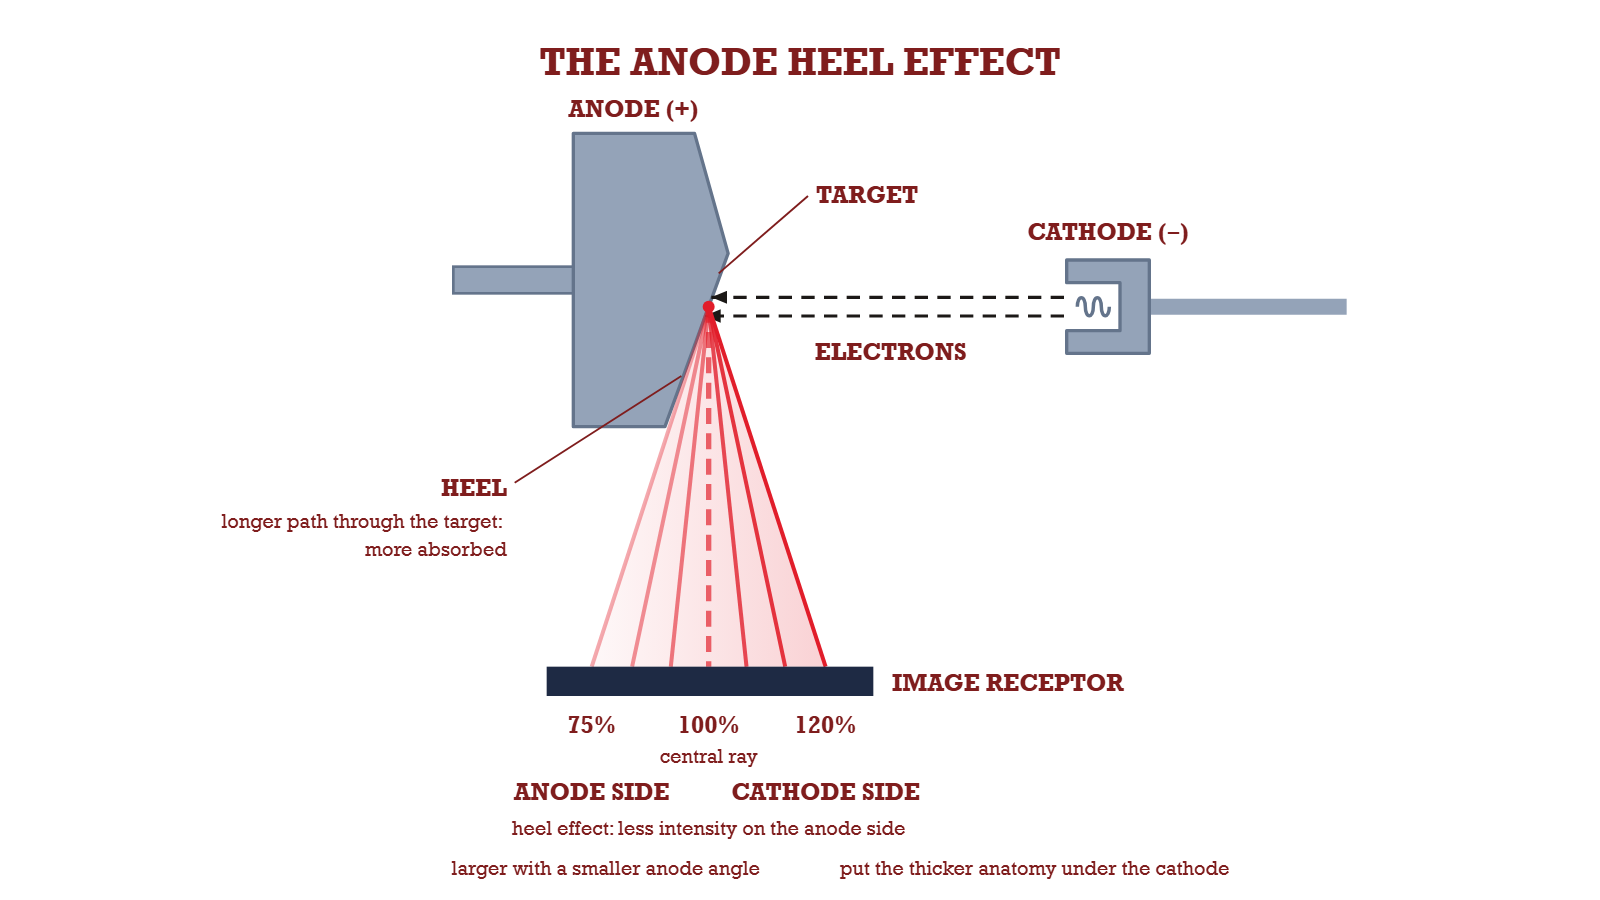
Image Production: Equipment Operation and Quality Assurance
This category has 25 scored questions now and from March 1, 2027.
9. During a QC check at 100 cm (40 in) SID, the edges of the light field and the x-ray field are misaligned by a total of 3 cm along the length of the field. Is this acceptable?
- A) Yes, the limit is 5% of SID
- B) No, the limit is 2% of SID
- C) Yes, the limit is 10% of SID
- D) No, the limit is 1% of SID
Answer: B. Federal rules (21 CFR 1020.31) limit total misalignment along the length or width to 2% of SID. At 100 cm, that is 2 cm, so 3 cm fails. (A) and (C) are too loose and would pass a unit that should be reported. (D) gets to “no” with the wrong limit.
Safety: Radiation Physics and Radiobiology
This category has 21 scored questions now and from March 1, 2027.
10. Which photon interaction is the main reason bone and soft tissue show contrast on an image?
- A) Compton scatter
- B) Pair production
- C) Photoelectric effect
- D) Coherent (classical) scatter
Answer: C. Photoelectric absorption rises with the cube of atomic number. Bone’s higher atomic number means it absorbs far more than soft tissue, which creates the difference you see. (A) Compton scatter is the main source of the scatter that reaches staff, and it adds fog rather than useful contrast. (B) Pair production needs more than 1.02 MeV, so it doesn’t happen in diagnostic imaging. (D) Coherent scatter happens mainly at very low energies and causes no ionization, so it plays little part here.
11. A stochastic effect of ionizing radiation is best described as:
- A) Having a threshold, with severity increasing with dose
- B) Probabilistic, with no threshold assumed
- C) Predictable and reversible
- D) Limited to skin reactions
Answer: B. For stochastic effects such as cancer, a higher dose raises the chance of the effect, not its severity, and no threshold is assumed. (A) describes deterministic effects, also called tissue reactions, such as skin erythema and cataracts. (C) Chance can’t tell you whether one person will be affected. (D) Skin reactions are deterministic.
12. A person receives an absorbed dose of 0.3 Gy from neutrons. Using a radiation weighting factor of 10, what is the equivalent dose?
- A) 0.03 Sv
- B) 0.3 Sv
- C) 3.0 Sv
- D) 30 Sv
Answer: C. Equivalent dose = absorbed dose × radiation weighting factor, so 0.3 Gy × 10 = 3.0 Sv. (A) divides instead of multiplying. (B) uses a factor of 1, which is right for x-rays but not for these neutrons. (D) is off by a factor of 10. A neutron’s real factor depends on its energy, from 5 to 20 in Sherer’s table, so use the one the question gives you. Outlines call this quantity “dose equivalent” and textbooks also say “equivalent dose.”
2027 note: the outline keeps this topic but changes its units reference from NCRP Report 160 to Report 184.
Safety: Radiation Protection
This category has 29 scored questions now and 25 from March 1, 2027.
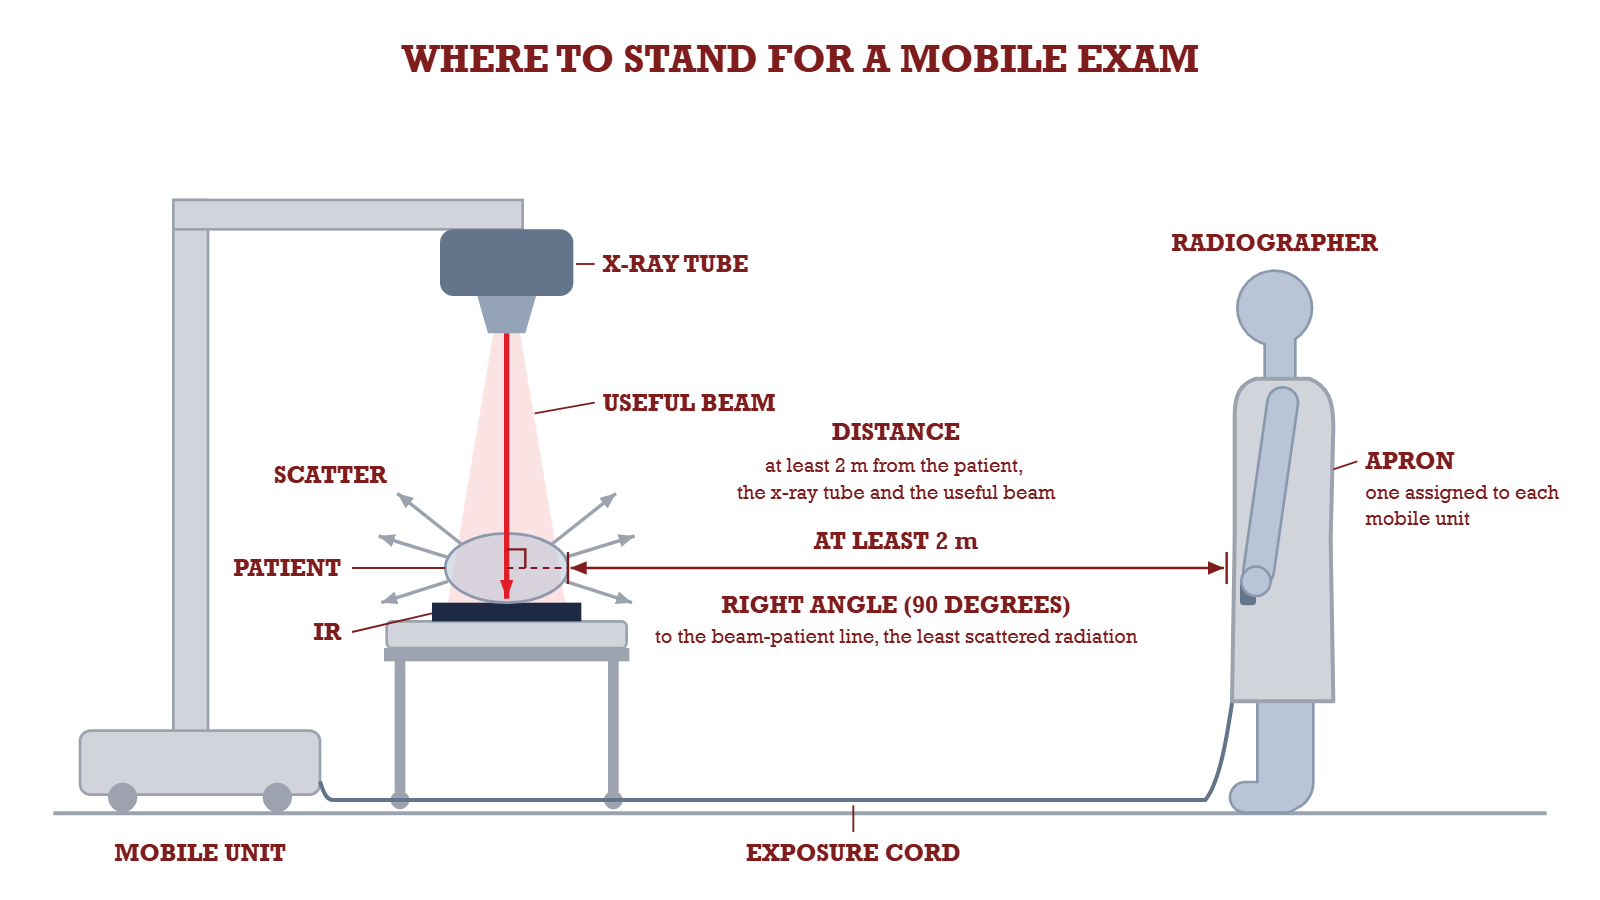
13. During a mobile chest exam, what is the minimum distance Sherer gives for the radiographer to stand from the patient, the tube and the beam?
- A) 1 m (about 3 feet)
- B) 2 m (about 6.5 feet)
- C) 3 m (about 10 feet)
- D) Any distance, as long as a lead apron is worn
Answer: B. Stand at least 2 m (about 6.5 feet) away. Sherer says the exposure cord must be long enough to let you do that. Wear an apron as well and stand at a right angle to the beam, where scatter is lowest. (A) is too close: doubling distance from 1 m to 2 m cuts intensity to one fourth. (C) is even better if you can manage it, but it isn’t the minimum. (D) An apron adds to distance. It doesn’t replace it.
14. The annual occupational whole-body dose limit in the United States is:
- A) 1 mSv (0.1 rem)
- B) 5 mSv (0.5 rem)
- C) 50 mSv (5 rem)
- D) 500 mSv (50 rem)
Answer: C. U.S. NRC rules (10 CFR 20) set 50 mSv (5 rem) a year for occupational whole-body dose, and that is the commonly taught number. (A) is the annual public limit. (B) is the embryo-fetus limit for the whole pregnancy once a pregnancy is declared. (D) is the annual limit for skin and extremities, not the whole body.
2027 note: the outline’s reference for personnel monitoring changes from NCRP Report 116 to Report 180. Check your program’s materials for any NCRP limit that differs from the NRC numbers. Our radiation protection guide covers the limits in more detail.
Not sure which section is weakest? Try the free practice test.
Procedures: Extremity
This category has 28 scored questions now and 30 from March 1, 2027.
15. A patient has wrist pain after falling on an outstretched hand. The routine PA, lateral and oblique are negative, but a scaphoid fracture is still suspected. The best added projection is:
- A) Carpal canal projection
- B) Stecher method
- C) AP oblique with medial rotation
- D) Lateral with radial deviation
Answer: B. The Stecher method lays the scaphoid’s long axis out flat so it isn’t foreshortened. Merrill’s raises the receptor and wrist 20° with a perpendicular CR, or angles the CR 20° toward the elbow. Bontrager’s raises the hand 20° on a sponge, adds ulnar deviation if possible and calls that the modified Stecher. It lists ulnar deviation with the CR 10 to 15° toward the elbow separately. (A) shows the carpal canal, not the scaphoid’s length. (C) isn’t on ARRT’s wrist list, whose oblique is the lateral oblique, and it doesn’t lengthen the scaphoid. (D) isn’t a listed projection: the deviation that helps the scaphoid is ulnar, not radial.
16. The AP mortise projection of the ankle requires the leg and foot to be rotated:
- A) 15 to 20° internally
- B) 30 to 40° internally
- C) 45° externally
- D) 90° (true lateral)
Answer: A. Internal rotation of 15 to 20° brings the intermalleolar line parallel to the receptor, which opens the mortise. (B) is the rotation for a medial oblique foot. (C) The lateral malleolus already sits 15 to 20° behind the medial one, so rotating externally moves it further the wrong way. Merrill’s does describe a 45° lateral rotation oblique, but not for the mortise, and it isn’t on ARRT’s ankle list. (D) is the lateral, a separate routine projection that doesn’t show the joint space this way.
Procedures: Thorax and Abdomen
This category has 20 scored questions now and 22 from March 1, 2027.
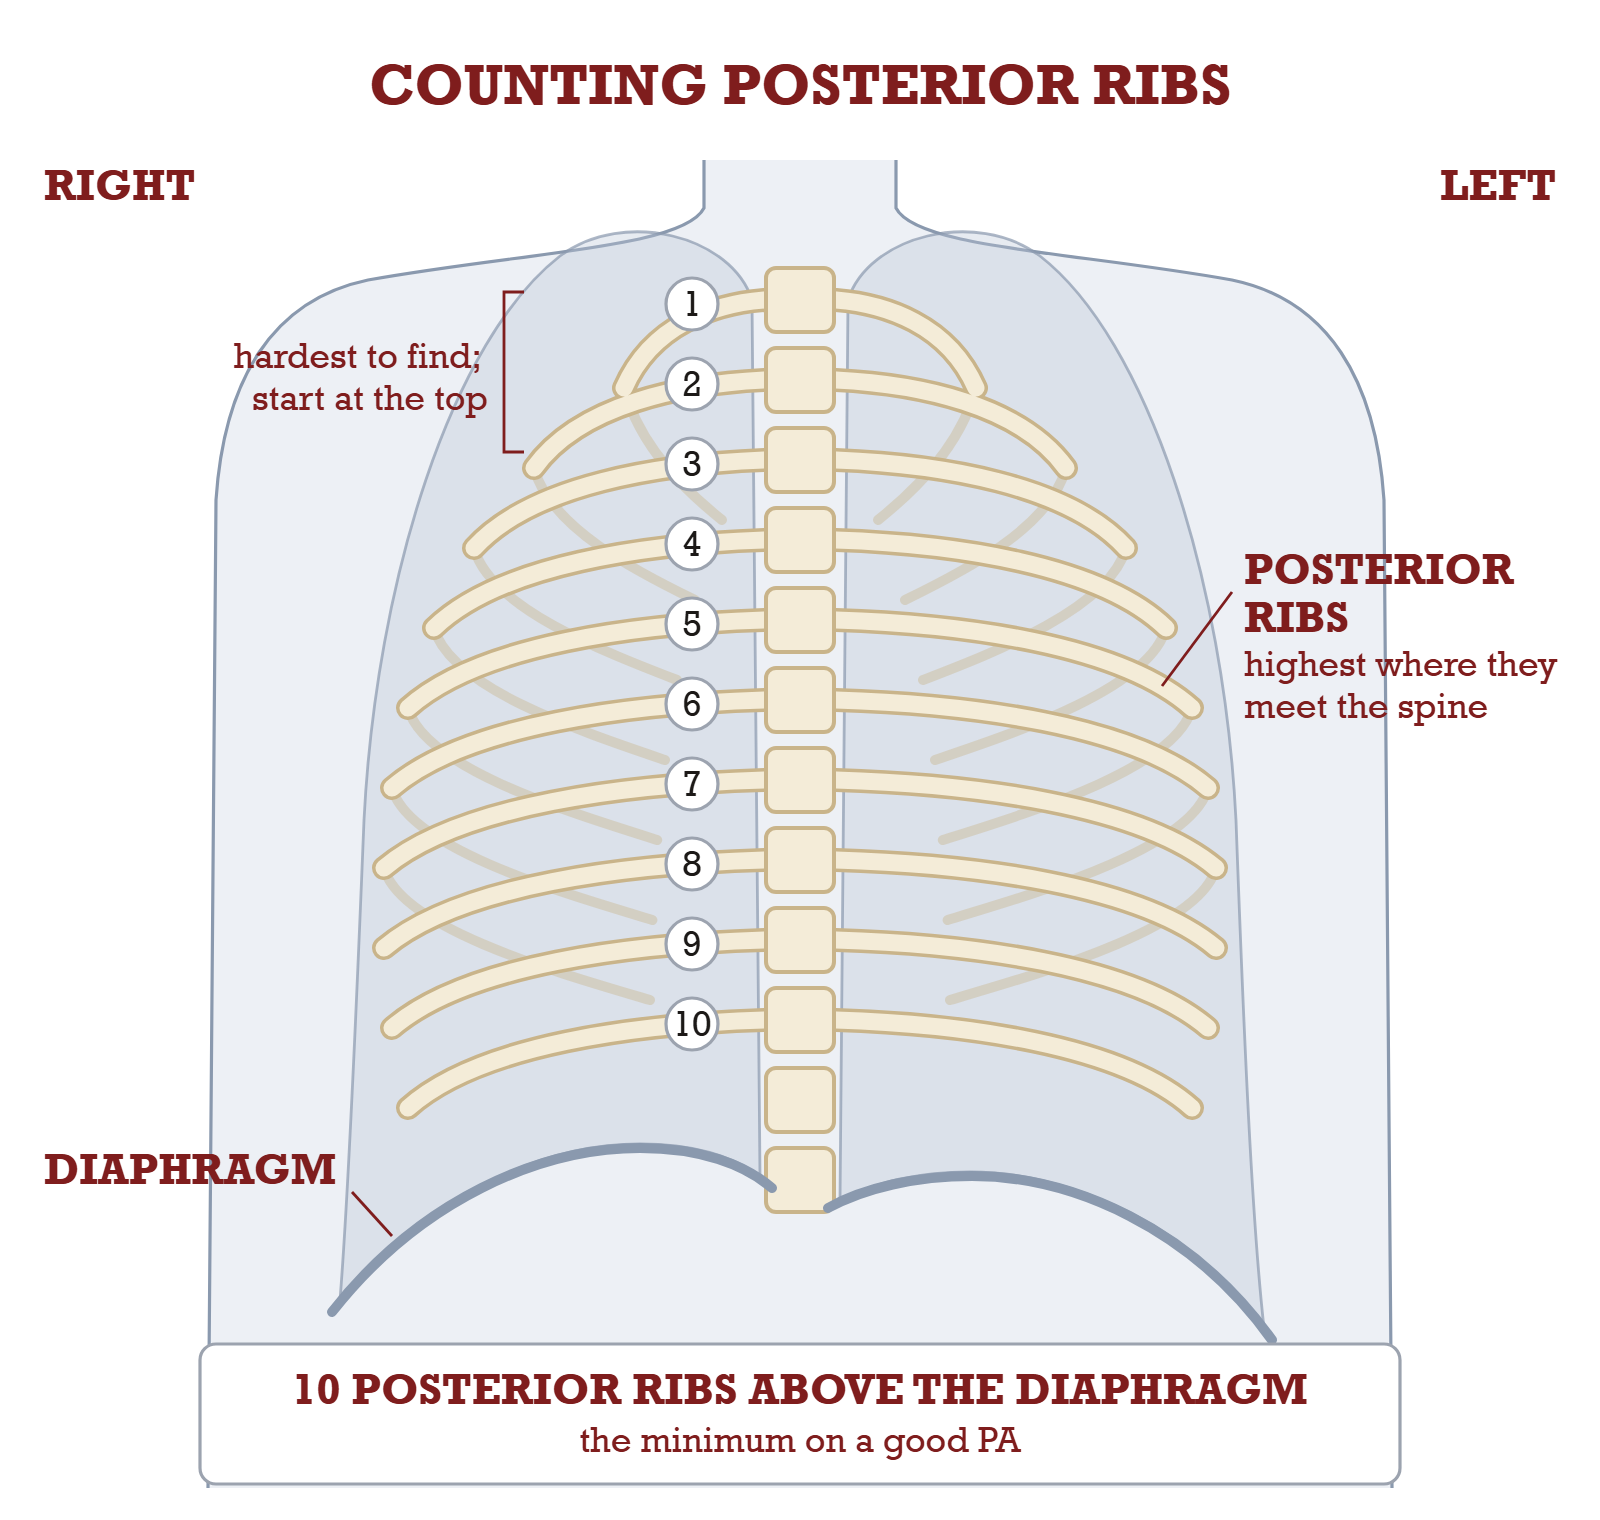
17. On a PA chest with good inspiration, what is the minimum number of posterior ribs you should see above the diaphragm?
- A) 6
- B) 8
- C) 10
- D) 12
Answer: C. At least 10 posterior ribs above the diaphragm is the commonly taught sign of good inspiration. (A) and (B) point to poor inspiration, which crowds the lung bases. (D) is too many to expect: 12 is the full count of rib pairs. Bontrager’s notes that many patients show 11, but the minimum stays 10.
18. During an upper GI series on a patient of average build, the duodenal bulb is best shown in profile in which position?
- A) Supine
- B) RAO, 40 to 70°
- C) Left lateral
- D) Prone
Answer: B. In the RAO, barium flows toward the pylorus and duodenum, and the bulb fills and shows in profile. Average (sthenic) builds usually need 45 to 55°. (A) Supine, barium pools in the fundus instead. (C) ARRT lists a left lateral for the esophagus and a right lateral for the upper GI series. (D) A straight PA shows the bulb clear of the pylorus only on slender builds.
Procedures: Head, Spine and Pelvis
This category has 18 scored questions now and 20 from March 1, 2027.
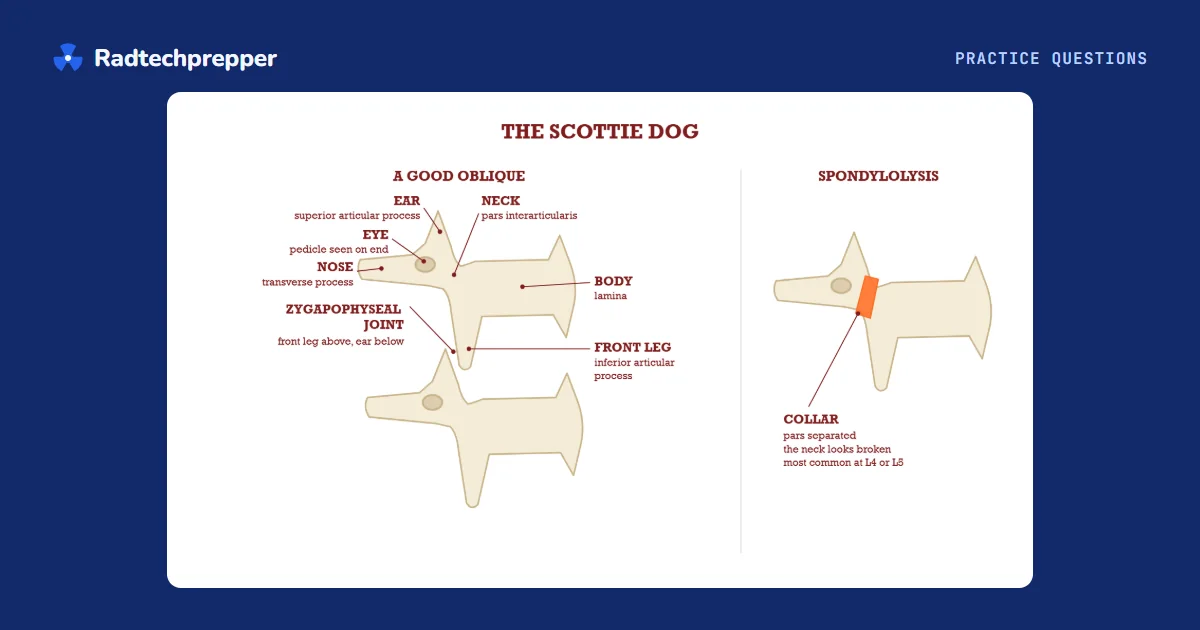
19. On a 45° posterior oblique of the lumbar spine, a “collar” on the Scottie dog’s neck represents:
- A) Spondylolisthesis
- B) Spondylolysis
- C) Disk herniation
- D) Compression fracture
Answer: B. The dog’s neck is the pars interarticularis. A collar means a break in the pars, which is spondylolysis. (A) is forward slip of one vertebra on another. Bontrager’s table lists AP and lateral lumbar spine and CT for it. (C) Radiographs show only the bony margins, so they don’t show the herniation itself. (D) is lost height in the vertebral body, and Bontrager’s table lists the same exams.
20. For the Towne method (AP axial skull), with the OML perpendicular to the receptor, the central ray is angled:
- A) 15° caudad
- B) 30° caudad
- C) Perpendicular to the IOML
- D) 25° cephalad
Answer: B. The Towne uses 30° caudad to the OML (37° if the IOML is the perpendicular line instead), which drops the dorsum sellae into the foramen magnum. (A) is the Caldwell, a PA axial. (C) is the SMV. (D) goes the wrong way: the Towne beam angles down toward the feet. A 25° cephalad angle belongs to the Haas, a PA axial that does a similar job with the patient prone or facing the receptor.
Want the reasoning behind more of these? Our Procedures guide covers the projections section by section.
What does your score mean?
This is our judgment, not a prediction. Twenty questions can’t tell you whether you will pass. ARRT also says “A score of 75 doesn’t mean you correctly answered 75% of the test items,” so don’t convert this score into an exam score.
- 16 to 20 correct: take a full timed mock next. It tells you far more than this sample.
- 11 to 15 correct: note which categories you missed, then drill those first.
- 10 or fewer correct: start with the chapters before you drill. A low score here is only a starting point.
Looking for a full schedule? Our 60-day study plan lays it out by week.
Where can you get more free ARRT practice questions?
The Radtechprepper free tier gives you 50 more questions, 1 200-question timed mock and 3 chapters (Skull, Elbow and Shoulder, Urinary), with no card. Those 3 chapters are all Procedures, so no Patient Care, Safety or Image Production chapter is free.
The full bank has 2,500+ questions (2,584 today; from March 1, 2027, generated mocks draw from 2,504, and category drills keep all 2,584), and every question has a written rationale. The 20 above explain all four options. Most rationales in the bank are shorter and focus on the right answer. See what changes in March 2027 if your exam date is close to that line.
Paid plans open soon: Monthly at $39 that renews until you cancel, a 90-Day Pass at $99 once that never renews, or Annual at $199 a year (about $16.58 a month) that renews until you cancel. They can’t be bought yet. Paid plans include a pass guarantee, with conditions, and a 30-day refund on your first Monthly or Annual purchase. That policy doesn’t list the 90-Day Pass.