Pediatric AEC errors: both underexposure and overexposure can happen
Key takeaways
- Part of the cell uncovered: the ACR-AAPM practice parameter says this can artificially shorten the exposure on a child, which can underexpose.
- Needed time shorter than minimum response time: likely overexposure, by our reasoning.
- Active cell outside the field: by our reasoning, the exposure can run to the back-up limit and overexpose.
- Windowing can't fix either one. Check the noise and the exposure indicator.
- Follow your department's pediatric technique chart.
The short answer: AEC on a small child can fail in either direction. If you learned “it only underexposes”, that is too narrow. The ARRT® outlines list “minimum response time” and “back-up timer” under AEC without saying which way either one fails. We read both as routes toward too much exposure.
What are the three failure routes?
The ACR-AAPM practice parameter gives the first route for children: partial coverage of the active cells can artificially shorten the exposure. The other two routes, and the “why” in the first row, are our reasoning from how AEC works.
| What happens | Why | Likely result |
|---|---|---|
| Part doesn’t fully cover the active cell | Less-attenuated beam reaches the cell, so it hits its preset level fast | Early stop, underexposed anatomy, more noise |
| Needed time is shorter than the minimum response time | The exposure can’t end soon enough | Overexposure |
| Active cell is outside the collimated beam | The cell gets little radiation and doesn’t stop the exposure | Runs to the back-up limit, overexposure |
Here is what else the sources say. Bushong says the exposure ends when the chamber’s charge reaches a preset level, and that the part must be placed over the device for proper exposure. AAPM Report 150 says a long minimum response time could limit AEC performance on thinner patients, without naming a direction. Its back-up timer test covers the receptor with lead to force the back-up. The ACR-AAPM practice parameter says AEC may miss the desired receptor dose when anatomy isn’t centered over the active cells, and that gonadal shields may substantially increase exposure if they cover the active cells. Scatter can also end an exposure early: Merrill’s describes scatter from the patient reaching the AEC device and ending a lateral thoracic spine exposure too early, and it lists close collimation among the ways to improve that image.
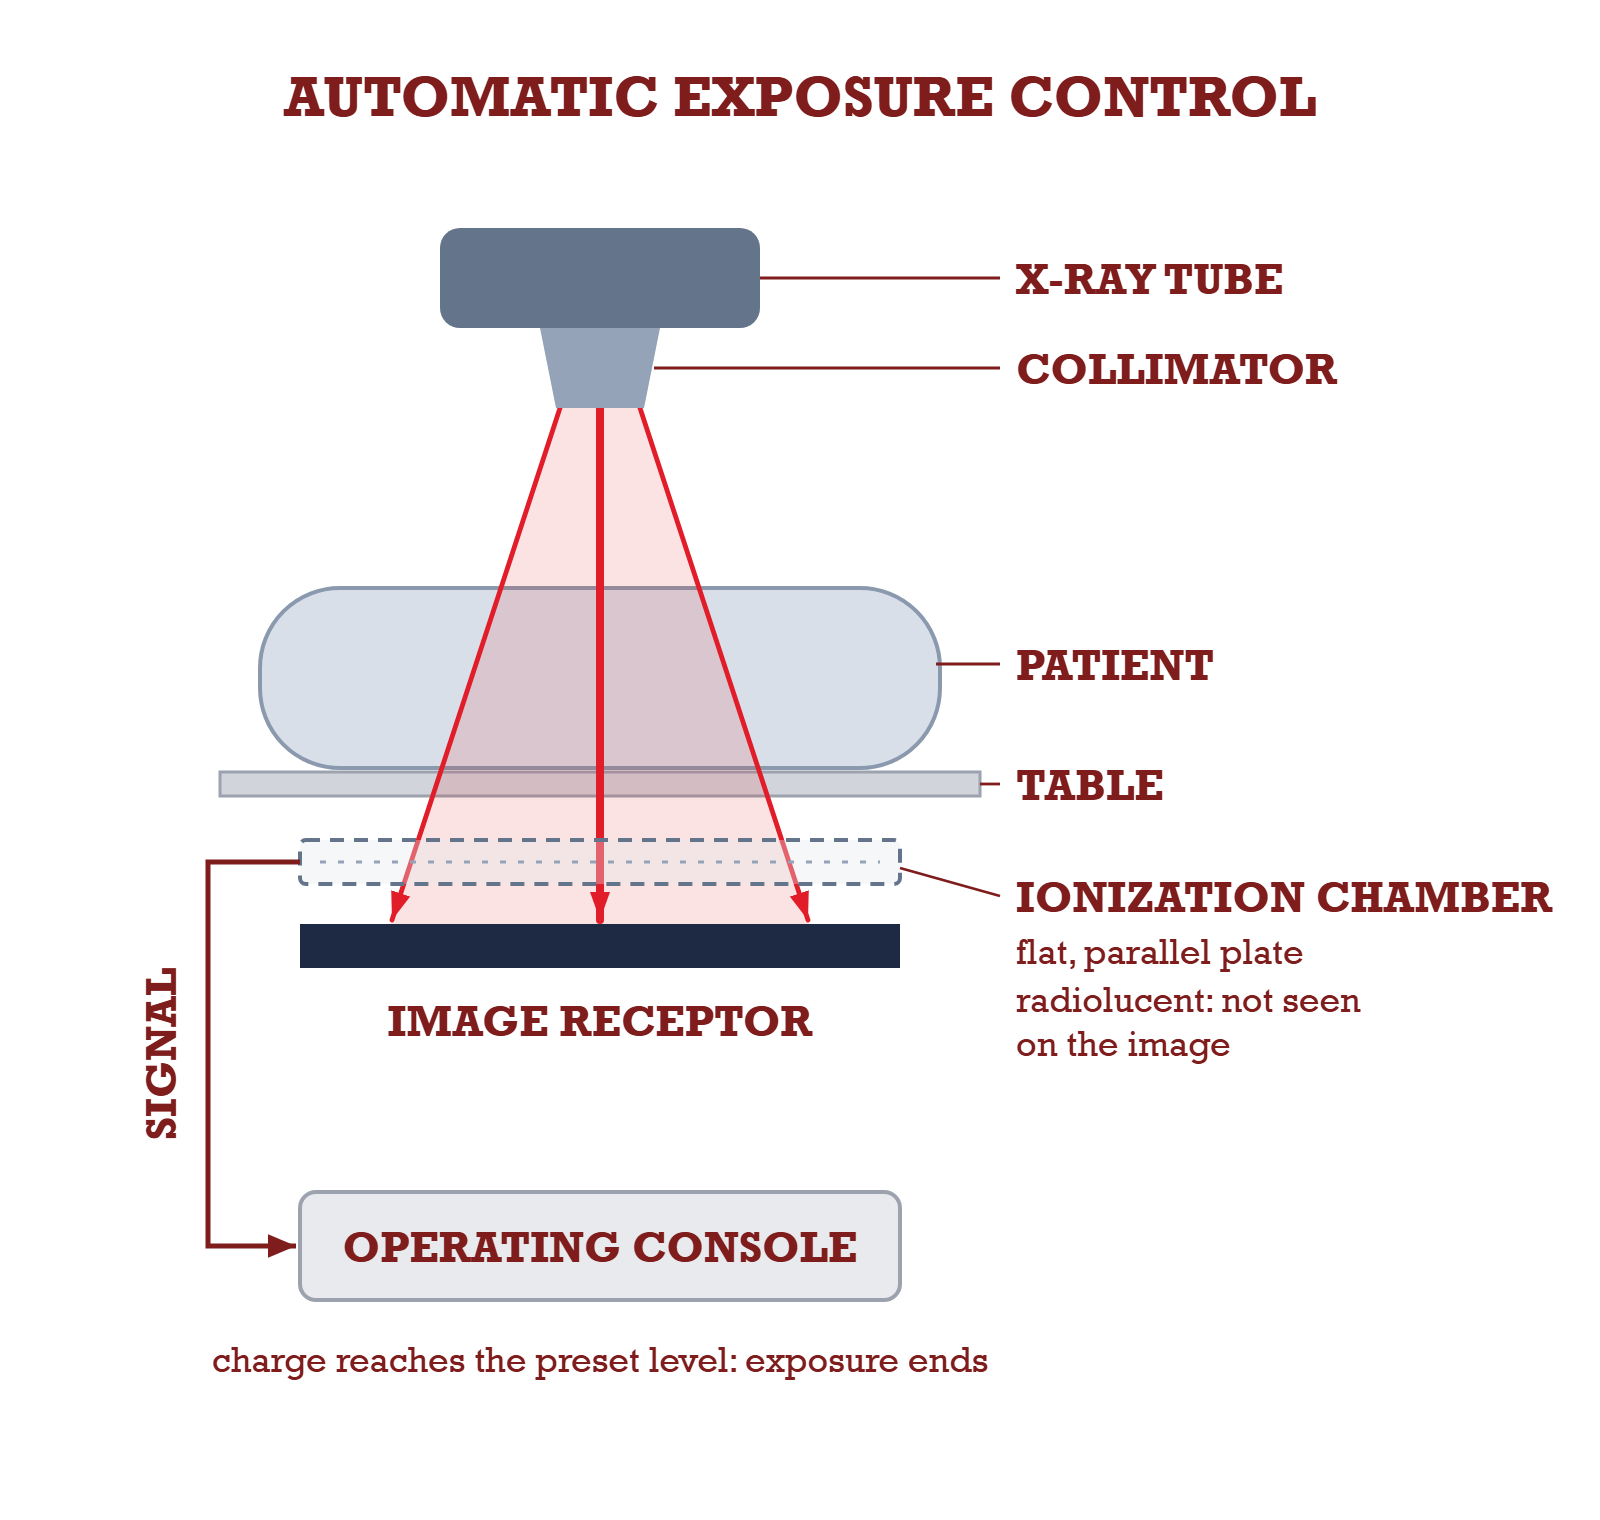
How short are these exposures?
Very short. AAPM Report 150 gives a thin patient’s PA chest at 120 kV and maximum mA as 1 to 3 ms. It expects a minimum response time of 3 ms or less on high-frequency generators, and says thin phantoms are the most common place thickness tracking goes wrong. A chest doesn’t take seconds.
What do you do about it?
- Check coverage: the anatomy must cover every active cell.
- Use the pediatric chart: Merrill’s refers to special charts for pediatric patients. Your department decides when AEC is used.
- Lower the mA: a lower mA means a longer exposure time, which moves it away from the minimum response time. That is our reasoning, and AAPM Report 116 describes AEC testing with mA adjusted to keep exposure times above 10 ms. Follow your protocol.
- Set the back-up sensibly: the AEC cell page covers back-up time. Federal rules limit AEC exposures at 51 kVp and above to 600 mAs or 60 kWs. Bushong calls this a safety override for when the AEC fails to stop the exposure. In our judgment it won’t protect a small child by itself.
How do you spot the error afterward?
Underexposure shows as noise. Overexposure may not show at all, because AAPM Report 116 says an overexposed digital image may not look dark. Read the exposure indicator, but use judgment: a large uncovered area can throw it off. Windowing can’t recover a bad exposure.
More in the Image Production guide, the Pediatric Radiography chapter and the Equipment QA set.
Frequently asked questions
Does AEC underexpose or overexpose small children?
It can do either. The ACR-AAPM practice parameter says partial coverage of the active cells on a child can artificially shorten the exposure, which can underexpose. By our reasoning, a very short required time or a cell outside the field can overexpose.
What is minimum response time?
The shortest exposure the AEC can reliably end. AAPM Report 150 expects 3 ms or less on high-frequency generators and says a long response time can limit AEC on thinner patients.
Can windowing fix an AEC error?
No. Windowing changes the display only. It can't add photons to an underexposed image or remove dose from an overexposed one.
Is there a body thickness where you must switch to manual technique?
We found no source for a fixed cutoff such as 12 cm. Follow your department's pediatric chart and protocol.
Sources
Found an error? Email [email protected] with the page and the source.
- AAPM Report 150, Acceptance Testing and Quality Control of Digital Radiographic Imaging Systems, 2024, sections 4.4.3, 4.4.10 and 4.4.12 Official
- AAPM Report 116, An Exposure Indicator for Digital Radiography, July 2009, PDF p.7, p.23 and p.73 Official
- ACR-AAPM-SIIM-SPR Practice Parameter for Digital Radiography, revised 2022, amended 2023, PDF p.8 and p.9 Guidance
- 21 CFR 1020.31(a)(3), automatic exposure controls Regulation
Know the answer. Now drill it.
Free tier includes 3 chapters, 50 practice questions and 1 full timed mock. No credit card.