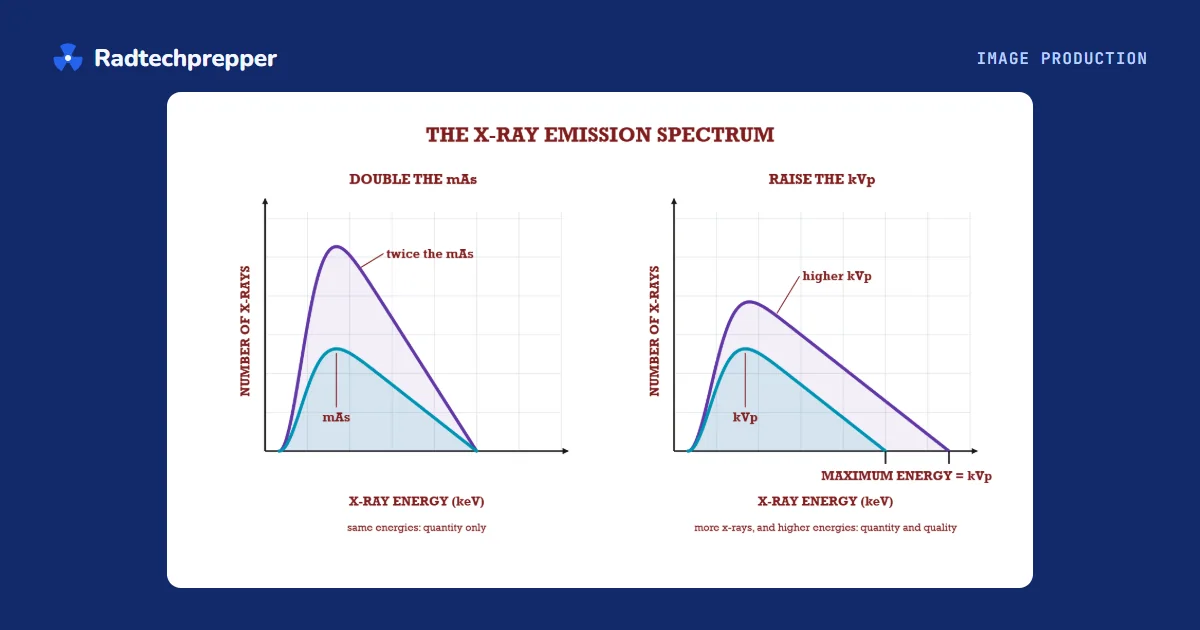
Here is the short version. mAs changes beam quantity only. kVp changes both quantity and quality. If you learned “kVp controls contrast, mAs controls density,” that line is a starting point for the ARRT® Radiography registry exam, but it leaves out too much. It hides that kVp also moves receptor exposure, and that a digital monitor can hide both kinds of technique error.
“Receptor exposure” is how much radiation reaches the image receptor. Older books call it density. ARRT’s outlines use receptor exposure, and keep “density” only for the AEC +1 and -1 control.
What is the difference between kVp and mAs?
| What it changes | mAs | kVp |
|---|---|---|
| Beam quantity (number of photons) | Yes, in direct proportion | Yes, with the square of the kVp ratio |
| Beam quality (energy, penetration) | No | Yes |
| Receptor exposure | Yes, marked on ARRT’s table | Yes, marked on ARRT’s table |
| Image contrast, 2027 table | Not marked | Marked |
| Subject contrast, 2027 table | Not marked | Marked |
A blank box on ARRT’s table means the pairing isn’t listed as an exam topic. It doesn’t prove the factor has zero effect.
What does mAs do?
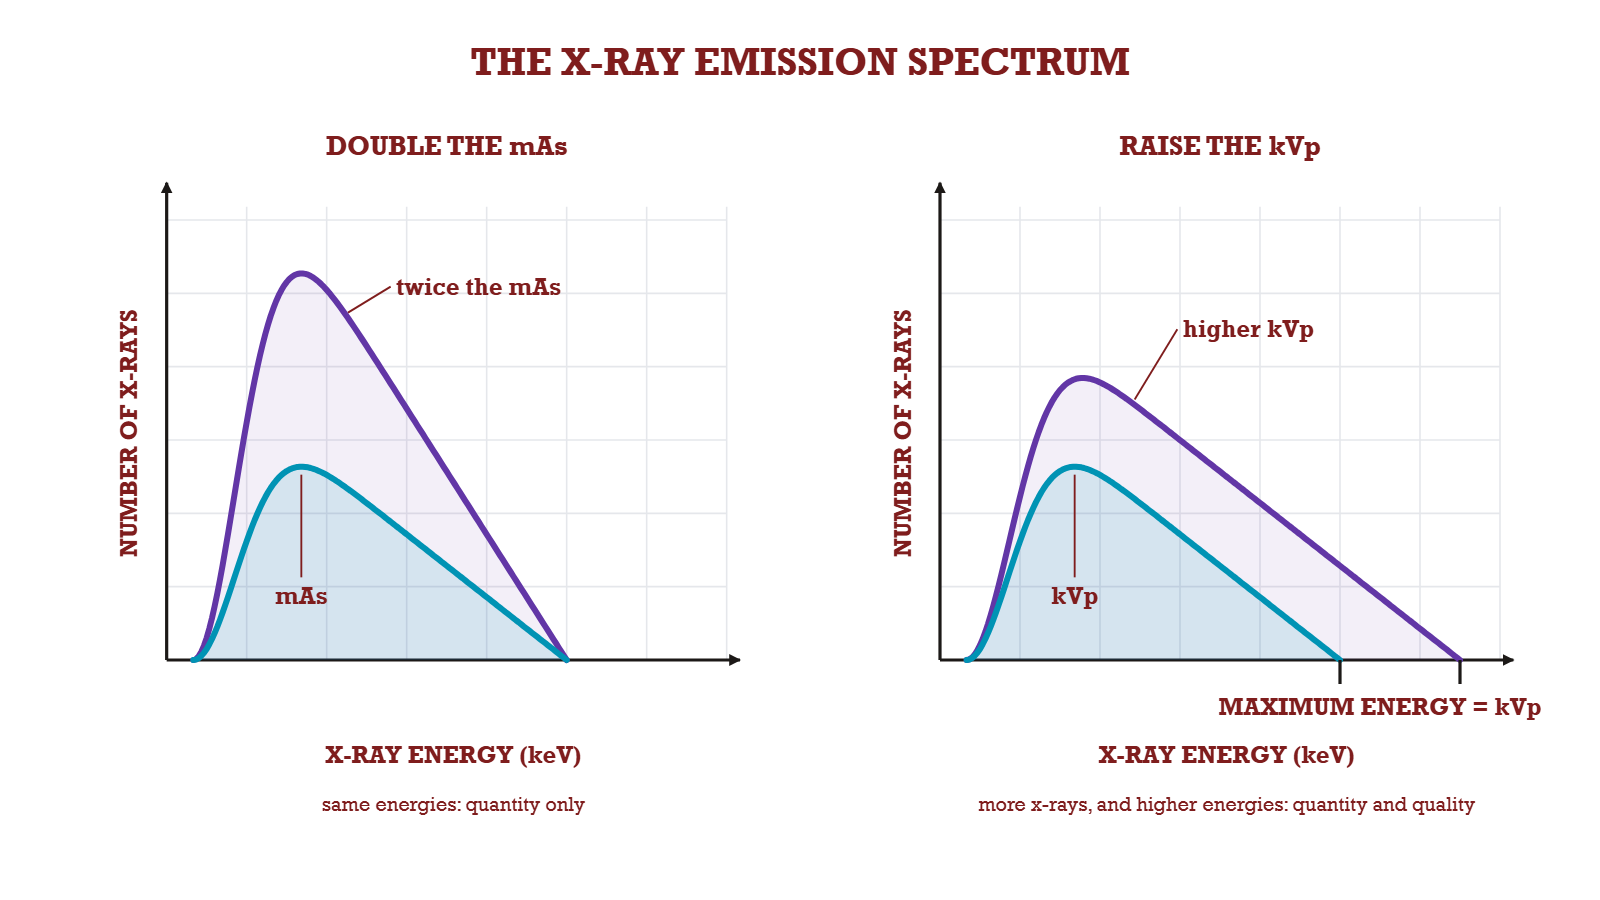
mAs is tube current in milliamperes multiplied by exposure time in seconds. It sets how many photons the tube makes. It doesn’t change their energy.
- Direct proportion: double the mAs and you double quantity, receptor exposure and patient dose.
- Reciprocity: 100 mA at 0.1 s and 200 mA at 0.05 s both give 10 mAs and the same exposure.
- Motion: a higher mA lets you shorten the time and keep the mAs, which is how you fight motion blur.
On a digital system, too little mAs shows up as noise, also called quantum mottle. Too much mAs may show up as nothing at all on the monitor, while the patient still takes the extra dose. AAPM Report 116 is direct about this: final brightness is controlled by post-processing, not by the exposure to the detector. So don’t read “brighter” or “darker” as a sign of mAs. Bontrager agrees that mAs doesn’t control digital brightness, and that overexposure isn’t readily evident on the monitor. Read the exposure indicator, whose scale varies by vendor.
What does kVp do?
kVp sets the highest photon energy in the beam. On the spectrum graph, the curve’s end point equals the kVp. Higher kVp also makes more photons, which is why it isn’t a pure quality control.
Raising kVp gives you:
- more photons, with quantity changing by the square of the kVp ratio (Bushong)
- more penetration, so more of the beam gets through the patient
- more scatter
- lower contrast, with a longer scale of grays
- higher receptor exposure
Lowering kVp reverses all of that. The practical trade is dose: for the same receptor exposure, higher kVp with lower mAs means lower patient dose.
Bontrager’s chest technique sits at 110 to 125 kV, so the beam gets through both lung and mediastinum. Our PA chest page has the positioning and a sample technique.
Does kVp still control contrast in digital imaging?
Yes, but “controls” needs care. Three things are true at once.
kVp still changes subject contrast. Subject contrast is created in the patient, before the beam reaches the receptor. Beam energy decides how differently each tissue attenuates. No software step adds information the beam never carried.
kVp still affects image contrast, though you may not see it. Image contrast depends on how much scatter reaches the receptor, then on the receptor and the processing. AAPM Report 150 says kV can strongly impact patient dose and image contrast, and that display algorithms tend to mask kV-related contrast changes. AAPM Report 116 adds that digital brightness and contrast are “often determined entirely by digital post-processing.” Bontrager says the same in its own words: kV has less direct effect on final digital contrast, because processing also sets it.
kVp isn’t the only contrast factor. ARRT’s 2027 table also marks OID, grids, tube filtration, beam restriction and patient factors for image contrast. So “kVp controls contrast” is too narrow, and “kVp doesn’t matter in digital” is wrong. The safe version is this: kVp is a main driver of subject contrast, and processing decides much of what you see on the monitor.
The classic example is Bushong’s aluminum step wedge. At 50 kVp and 60 mAs only five steps are visible: short scale, high contrast. At 90 kVp and 10 mAs all 13 are visible: long scale, low contrast. Notice that mAs changed along with kVp. That comes from Bushong’s screen-film chapter. On a digital monitor, processing also shapes the final look.
To change the displayed contrast of an image you already took, use window width, not a new exposure. That changes the display only, and the patient’s dose stays the same. Our Image Production guide covers windowing and the look-up table.
Not sure which section is weakest? Try the free practice test.
What is the 15% rule?
Raise kVp by 15% and receptor exposure roughly doubles, the same as doubling mAs. Lower kVp by 15% and it roughly halves. So you can trade one for the other:
- +15% kVp: halve the mAs to keep receptor exposure about the same.
- -15% kVp: double the mAs to keep receptor exposure about the same.
Starting technique
70 kVp
20 mAs
kVp up 15%, mAs halved
80 kVp
10 mAs
Result: about the same exposure at the receptor, from a more penetrating beam.
70 x 1.15 = 80.5, usually rounded to 80. A rule of thumb, not an exact law.
The chart uses 70 kVp at 20 mAs against 80 kVp at 10 mAs. A step of 70 to 80 is about 14%, close enough to teach the idea. For exact arithmetic, 80 kVp at 30 mAs becomes 92 kVp at 15 mAs, which is Bushong’s own example.
Why does 15% do so much? Tube output rises by only about 32% (1.15 squared is about 1.32). Bushong says doubling output with kVp alone could take as much as a 40% rise. The rest of the gain at the receptor comes from more photons getting through the patient. Bushong puts this as intensity rising with kVp squared at the patient and kVp to the fifth power at the receptor, and 1.15 to the fifth is about 2.
The dose logic in simple numbers: 1.32 times the output, at half the mAs, is about 0.66. Bushong’s worked example gets the same factor for entrance skin exposure, about a third less. Bontrager’s digital example reports about 22% less entrance skin dose, and it says to consult the radiologist and medical physicist before raising kVp across the board. So the saving is real, and the size depends on the case.
The rule is a rule of thumb, and the books word its limits differently. Bushong says about 7 kVp does the job at 50 to 60 kVp, and it may take 15 kVp above about 100 kVp. Bontrager says 8 to 10 kV at 50 to 70 kV, and 12 to 15 kV at 80 to 100 kV. The two techniques aren’t identical images, because scatter changes along with the kVp. Bushong’s film chapter says contrast changes too. Its digital note says there is little change in contrast on digital receptors, while AAPM Report 150, quoted above, says kV can strongly affect image contrast and display algorithms tend to mask it. If you only want to change receptor exposure, Bushong says to change mAs instead. It also gives a smaller 5% version for a modest contrast change: 5% more kVp with 30% less mAs.
When should you change kVp, and when mAs?
Follow your department’s chart and protocols first. This table is the reasoning behind them.
| Situation | What to change | Why |
|---|---|---|
| Exposure indicator low, image noisy | More mAs | Noise means too few photons |
| Exposure indicator high, image looks fine | Less mAs next time | Extra dose with no need for it |
| Motion blur | Higher mA, shorter time, same mAs | Reciprocity |
| Beam isn’t getting through the part | More kVp, then reduce mAs with the 15% rule | Penetration is a quality problem |
| Thicker patient, variable-kVp chart | Add 2 kVp per cm (Bushong) | The chart holds mAs fixed |
| Thicker patient, fixed-kVp chart | Raise mAs as the chart says | The chart holds kVp fixed |
| Additive disease (pleural effusion, atelectasis) | More exposure | It attenuates more |
| Destructive disease (emphysema, osteoporosis) | Less exposure | It attenuates less |
| Image looks gray, exposure indicator on target | Check menu, collimation and window width first | The cause may be processing or scatter, not technique |
Three things to watch.
Thickness. Bushong says fixed-kVp charts have largely replaced variable-kVp charts. On a variable-kVp chart, it says you must measure the part accurately. On a fixed-kVp chart that groups parts as small, medium and large, it says measurement isn’t critical, though its general rule is that patient thickness should not be guessed. Thickness isn’t the only factor either: Bushong says the thorax and abdomen may have the same thickness and still need considerably different techniques, and that the chest has high subject contrast and the abdomen low. Its fixed-kVp method takes mAs down 30% for small parts and up 30% for large ones, or sets a value for every 2 cm, which it calls more accurate than the small, medium and large labels. You may see “double mAs for every 4 to 5 cm” elsewhere. We searched Bushong, Bontrager, Merrill’s, Sherer and Ehrlich and Coakes, and none states it as a worded rule. Bushong’s Table 13-5, a fixed 80 kVp AP abdomen chart, does double mAs about every 4 cm (15 to 30, 22 to 45, 30 to 60, 45 to 90, 60 to 120). Treat that as a pattern in one table, and follow your department’s chart.
Pathology. Pneumothorax is a known trap. Bushong’s table lists it as radiolucent, but Bontrager’s chest table prints generally no adjustment. The books differ, so read our pathology chapter before you memorize one rule for every condition.
The 30% figure is a film rule. Bushong says mAs must change by about 30%, and kVp by about 4%, for a perceptible density change on film. Bontrager says at least 25% to 30% for mAs. On a digital monitor, processing hides that change, so read the exposure indicator rather than looking for a visible difference.
With AEC, you still set kVp and mA and choose the cells, and the AEC decides when to stop. It controls time. A well-calibrated AEC can also cover up a kVp problem by keeping receptor exposure steady, which is one reason kVp is tested separately in QC.
Worked examples
These use sample numbers to show the reasoning. They aren’t protocols.
A chest with a deviation index of +3
You shoot a PA chest at 120 kVp and 2.8 mAs. The image looks fine. The deviation index (DI) reads +3, which is about twice the target exposure.
- Don’t repeat it. AAPM Report 116 says to repeat an overexposed image only if relevant anatomy is clipped or “burned out.”
- Don’t rely on windowing. It changes the look and leaves the dose as it was.
- Next time: use 1.4 mAs. Same beam energy, half the quantity, DI near 0.
A knee with a DI of -3.2
You shoot a lateral knee at 85 kVp and 2.5 mAs. The image is grainy and the DI is -3.2, a little under half the target. AAPM’s suggested limits list “repeat” below -3. Follow your department’s limits. Changing mAs is the direct fix for noise, so double it to 5 mAs and leave kVp alone. DI should land near 0. Check centering and collimation too, because either can give a false reading.
The registry-style math
Try these practice-style problems. They’re ours, not real ARRT items.
1. The technique is 80 kVp at 30 mAs. You raise kVp to 92. What mAs keeps receptor exposure about the same? Answer: 15 mAs. 92 is 15% above 80.
2. You need higher subject contrast at about the same receptor exposure. The technique is 80 kVp at 15 mAs. Answer: 68 kVp at 30 mAs. Patient dose goes up, which is the cost.
3. Which factor changes beam quality: mA, exposure time, mAs or kVp? Answer: kVp.
4. You double mAs and leave kVp alone. What happens to the average energy of the beam? Answer: nothing. Quantity doubles.
More like these are in the Image Acquisition practice set. It has 367 questions today and 326 from March 1, 2027, and every question has a written rationale.
Did the March 2027 outline change kVp and mAs?
Yes, in a way that affects how you study.
| Column on the factor table | Through Feb 28, 2027 | From Mar 1, 2027 |
|---|---|---|
| Receptor exposure | mAs and kVp both marked | mAs and kVp both marked |
| Image contrast | No such column | kVp marked, mAs not |
| Subject contrast | No such column | kVp marked, mAs not |
| Spatial resolution | Neither marked | Neither marked |
| Distortion | Neither marked | Neither marked |
If you test before March 1, 2027, contrast is still on your outline under image evaluation and contrast resolution, so learn it either way. If you test after, learn kVp’s three boxes and mAs’s single box. The Image Acquisition and Evaluation count stays at 26 questions. See how this fits your full plan in how to pass the ARRT registry.
What should you learn next?
- Inverse square law: double the SID and intensity falls to one quarter.
- Keeping exposure when SID changes: mAs₂ = mAs₁ × (SID₂ ÷ SID₁)². Going from 102 cm to 183 cm needs about 3.2 times the mAs.
- Grid conversion: Bushong’s printed averages are no grid 1, 5:1 = 2, 8:1 = 4, 12:1 = 5, 16:1 = 6. The true factor rises with kVp, and a grid raises patient dose.
- Dose: kVp, mAs and AEC are also listed under minimizing patient exposure in our Radiation Protection guide.
The chapter version is Radiographic Quality. The app also has 35 formulas with 19 drill problems. Sign up free for 3 chapters (all Procedures), 50 questions and 1 200-question timed mock, no card. Paid plans open soon.