Image Production is the second-largest section of the ARRT® Radiography registry exam, after Procedures. It is 51 of 200 scored questions, and that count doesn’t change on March 1, 2027. Much of it comes down to one skill: knowing which control moves which part of the image.
Not sure which section is weakest? Try the free practice test.
What does ARRT Image Production cover?
| Subsection | Through Feb 28, 2027 | From Mar 1, 2027 |
|---|---|---|
| Image Acquisition and Evaluation | 26 | 26 |
| Equipment Operation and Quality Assurance | 25 | 25 |
| Total | 51 | 51 |
The counts hold steady, but the outline underneath them moves.
| Topic | 2022 outline | 2027 outline |
|---|---|---|
| Factor table | 3 columns | 5 columns: adds image contrast and subject contrast |
| CR plate and plate reader, sampling frequency, radiation fog, erasure thoroughness | Listed | Gone |
| Compensating filters | Listed | Gone |
| Virtual grids, Nyquist frequency | Not listed | Listed |
| Informatics | PACS, DICOM | Adds MIMPS, security and confidentiality, teleradiology |
Film and screens appear in neither outline, so old film-processing content isn’t worth your time. “Density” survives only as the AEC +1 and -1 control. Use “receptor exposure”, which is what older books mean by density. If your test date falls on or after March 1, 2027, skip the CR details. The words “plate calibration” and “plate uniformity” do stay under receptor QC.
Which factor changes what?
This is ARRT’s own table from page 6 of the 2027 outline. An X marks a topic covered on the exam. A blank means the pairing isn’t listed, not that the factor has no effect.
| Factor | Receptor exposure | Image contrast | Subject contrast | Spatial resolution | Distortion |
|---|---|---|---|---|---|
| mAs | X | ||||
| kVp | X | X | X | ||
| OID | X | X | X | ||
| SID | X | X | X | ||
| Focal spot size | X | ||||
| Grids | X | X | |||
| Tube filtration | X | X | X | ||
| Beam restriction | X | X | |||
| Motion | X | ||||
| Anode heel effect | X | ||||
| Patient factors | X | X | X | X | |
| Angle (tube, part, receptor) | X | X | X |
Through February 28, 2027, the table has three columns only: receptor exposure, spatial resolution and distortion. kVp and mAs each have just the receptor exposure box there. Contrast still appears elsewhere on that outline, so learn it either way.
How do kVp and mAs affect the image?
mAs changes beam quantity only. kVp changes both quantity and quality.
mAs sets how many photons the tube makes. Double it and you double quantity, receptor exposure and patient dose. Too little shows up on a digital image as noise, also called quantum mottle.
kVp sets photon energy and also raises quantity. More kVp means more penetration, more scatter, lower contrast and higher receptor exposure.
Be careful with old shortcuts. kVp is a main driver of subject contrast, but it isn’t the only factor marked for image contrast. On digital systems, processing decides much of what you see. AAPM Report 150 says display algorithms tend to mask kV-related contrast changes. So kVp still matters, and you often can’t judge it by eye. Our kVp vs mAs guide works through this with examples.
The 15% rule: raise kVp by 15% and receptor exposure roughly doubles, the same as doubling mAs, so you can halve mAs. Lower kVp by 15% and it roughly halves, so you double mAs. Tube output itself doesn’t double. Bushong’s film chapter says the kVp change also alters contrast, so to change exposure alone, change mAs. Its digital note says there is little change in contrast on digital receptors, while AAPM Report 150 says kV can strongly affect image contrast and display algorithms tend to mask it. It’s a rule of thumb, and Bushong and Bontrager give different kVp steps at the low and high ends.
Starting technique
70 kVp
20 mAs
kVp up 15%, mAs halved
80 kVp
10 mAs
Result: about the same exposure at the receptor, from a more penetrating beam.
70 x 1.15 = 80.5, usually rounded to 80. A rule of thumb, not an exact law.
AEC ends the exposure once enough radiation reaches the active cell. You still choose the cells, so learn which AEC cell to use on a PA chest and how AEC fails on small children.
How does SID change exposure?
Intensity falls with the square of the distance. Double the SID and you have one quarter of the intensity.
To keep the same receptor exposure when SID changes:
mAs₂ = mAs₁ × (SID₂ ÷ SID₁)²
Example: 4 mAs at 183 cm (72 inches) becomes 4 × (102 ÷ 183)², or about 1.2 mAs at 102 cm (40 inches).
SID affects spatial resolution and distortion too. A long SID reduces magnification, which is one reason a PA chest uses about 183 cm.
The anode heel effect also changes exposure across the field. Intensity is greater on the cathode side, so put the thicker part under the cathode.
How do filtration and half-value layer work?
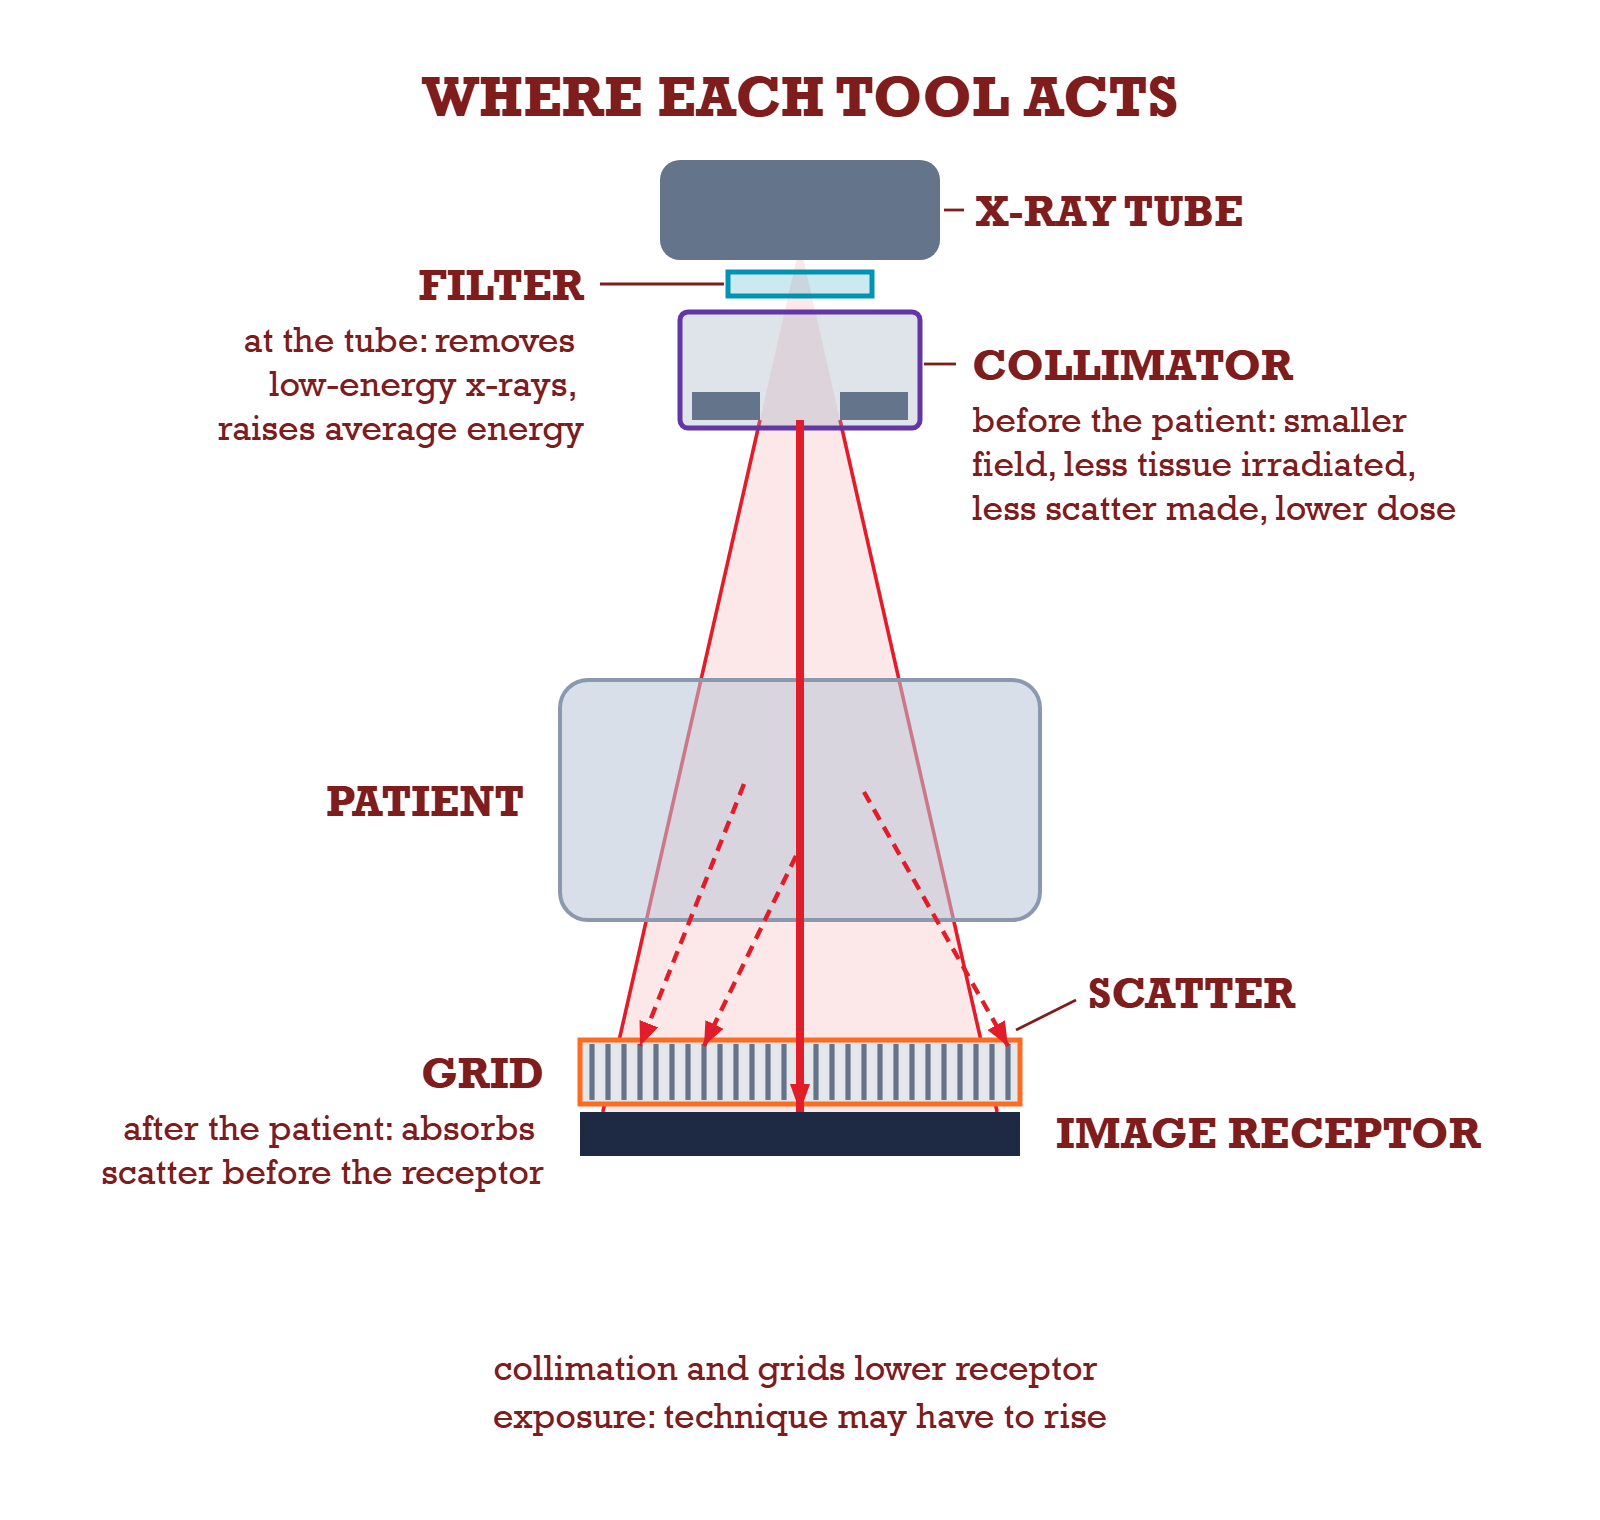
Filtration removes low-energy photons that would be absorbed in the patient and never reach the receptor. It raises beam quality and lowers beam quantity.
Sherer gives total filtration of at least 2.5 mm Al equivalent above 70 kVp, and 1.5 mm from 50 to 70 kVp on fixed units. Bushong’s typical build is about 0.5 mm inherent, 1.0 mm added and 1.0 mm from the collimator mirror.
Half-value layer (HVL) is the thickness of material that cuts air kerma rate to half. It isn’t the same number as filtration. The federal minimums in 21 CFR 1020.30(m) are:
| Measured kVp | Made before June 10, 2006 | Made on or after June 10, 2006 |
|---|---|---|
| 70 | 1.5 mm Al | 1.8 mm Al |
| 80 | 2.3 mm Al | 2.9 mm Al |
| 90 | 2.5 mm Al | 3.2 mm Al |
| 100 | 2.7 mm Al | 3.6 mm Al |
What does collimation do?
A smaller field irradiates less tissue, so it lowers patient dose and makes less scatter, which raises contrast. It can also need a small technique increase.
On digital systems, collimation does a third job: it helps the software find your exposure field. Bushong asks for four distinct collimated margins, says three usually works, and warns of artifacts with fewer than three. A recognition error can leave the image very dark, very light or very noisy.
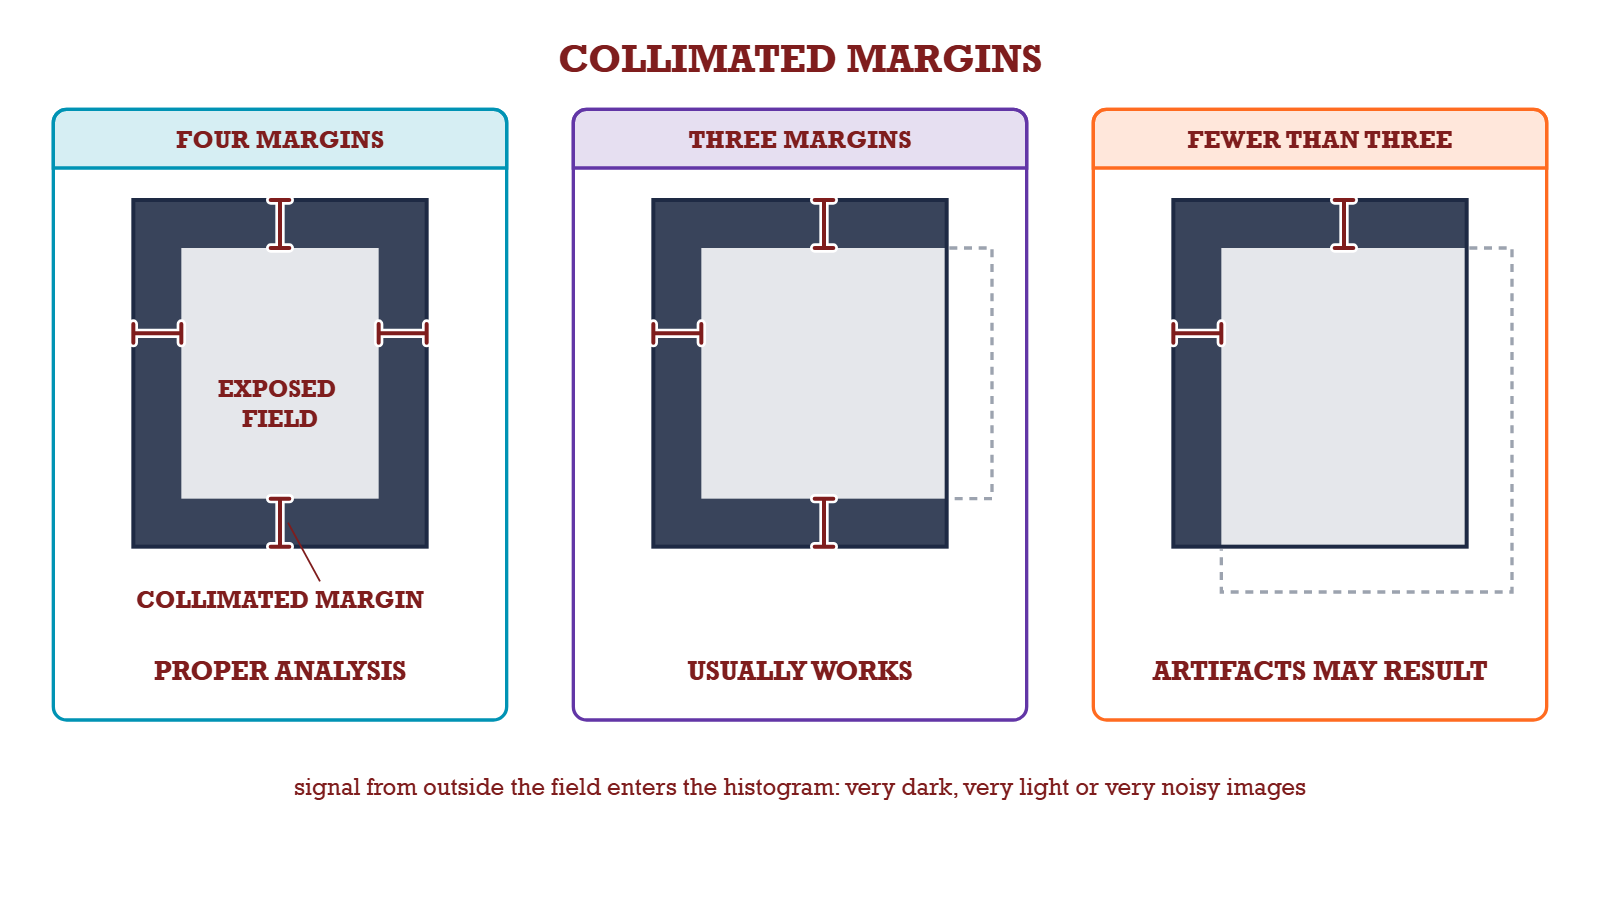
Bontrager’s general rule is also four sides when the receptor is large enough, but its digital guidance for lower limbs accepts a minimum of two parallel borders. So the books agree on the goal and differ on the floor. Aim for four, and treat fewer than three as a risk to check.
Federal limits worth knowing, from 21 CFR 1020.31:
- The light field and x-ray field must agree within 2% of the SID.
- With positive beam limitation (PBL), length or width can’t differ from the receptor by more than 3% of the SID, and the two differences together can’t exceed 4%.
Electronic cropping doesn’t replace collimation, because the patient was already exposed. ARRT also lists “manipulation of electronic data”, including cropping or masking off anatomy, as a legal issue in Patient Care.
How do grids work, and what are the cutoff errors?
A grid is lead strips with radiolucent interspaces. It absorbs scatter before it reaches the receptor. It raises contrast and raises patient dose. Bontrager generally recommends one for parts thicker than 10 cm.
Grid ratio = strip height ÷ interspace width. A higher ratio stops more scatter, needs more exposure and forgives centering errors less.
Grid conversion: new mAs = old mAs × (new factor ÷ old factor). These are the values Bushong prints as averages and uses for its technique table. The true factor rises with kVp: at 70 kVp Bushong lists 8:1 as 3 and 16:1 as 4, and at 120 kVp it lists them as 4 and 6.
| Grid | Factor |
|---|---|
| No grid | 1 |
| 5:1 | 2 |
| 8:1 | 4 |
| 12:1 | 5 |
| 16:1 | 6 |
Example: 10 mAs on an 8:1 grid becomes 10 × (6 ÷ 4) = 15 mAs on a 16:1 grid.
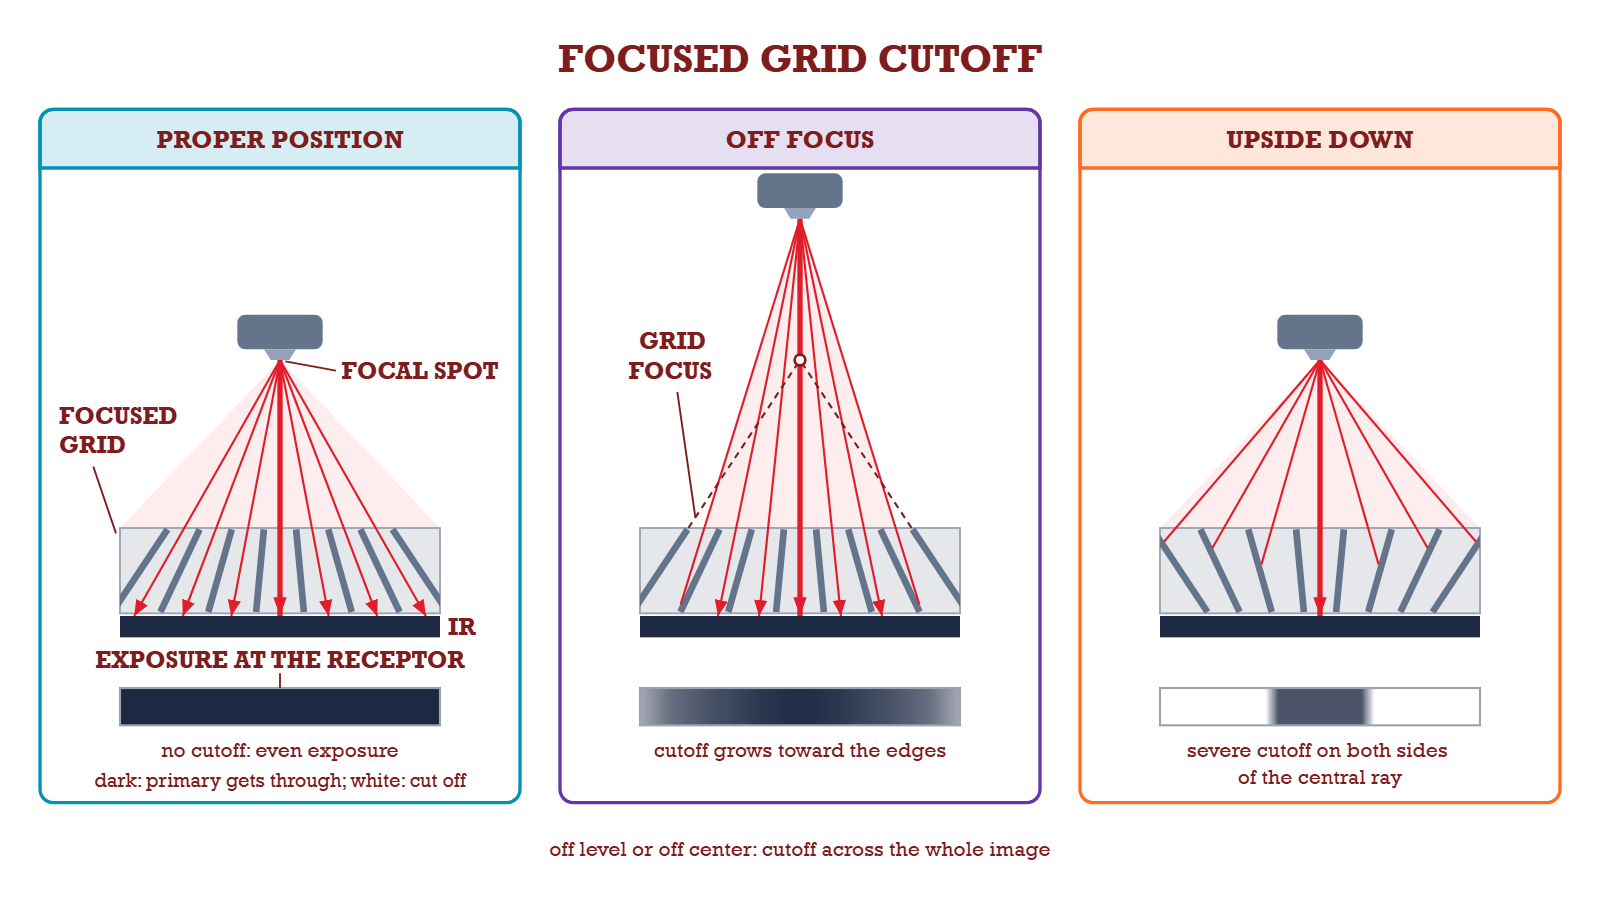
Grid cutoff means primary x-rays are absorbed, so that part of the image loses exposure.
- Off-level: cutoff across the whole image.
- Off-center: loss across the whole image.
- Off-focus (SID outside the grid’s range): cutoff grows toward the edges, center normal.
- Upside-down focused grid: severe cutoff toward both edges, normal center.
- Off-center and off-focus together: dark on one side, light on the other.
This list follows Bushong. Bontrager’s figure caption describes off-focus as an overall loss of density rather than an edge pattern, so the books differ there. On a digital image, Bontrager says cutoff shows as lower contrast and a lower exposure indicator.
Air gap: Bushong moves the receptor 10 to 15 cm from the part, which lets much of the scatter miss it, so contrast improves with no grid. OID is marked for image contrast on the 2027 table. ARRT gives no reason, but Bushong explains the mechanism: with larger OID, less scatter reaches the receptor. The cost is magnification with focal-spot blur. Technique is about that of an 8:1 grid, so dose is higher than with no grid, and the method works less well at high kVp. Bontrager cites a different case: on a 10 cm part, a 25 cm (10-inch) gap cleans up scatter about as well as a 15:1 grid, with less benefit on a 20 cm part.
Virtual grids are new on the 2027 outline, listed next to focused grids. The outline doesn’t define them. Merrill’s describes “grid-less imaging” on mobile DR as software that estimates the scatter and subtracts it from the raw image. It doesn’t use the words virtual grid, so that is the closest textbook description we found.
What affects spatial resolution and distortion?
Spatial resolution is recorded detail. A small focal spot, long SID and short OID sharpen the image. Motion blurs it. More mAs won’t fix blur.
On a digital receptor, detector element size sets a limit of its own. The 2027 outline names pixel size and pitch, detector element fill factor, matrix size, Nyquist frequency and MTF. AAPM Report 150 gives Nyquist frequency as 1 ÷ (2 × pixel spacing), so a 0.125 mm pitch gives 4 line pairs per mm.
Distortion comes in two types:
- Size (magnification): set by SID and OID. Magnification = SID ÷ SOD.
- Shape (foreshortening, elongation): set by the angle of the tube, part or receptor.
How do direct and indirect digital receptors differ?
The question is whether light appears in the middle.
- Direct conversion: amorphous selenium turns x-rays straight into charge.
- Indirect conversion: a scintillator such as cesium iodide turns x-rays into light, then an amorphous silicon layer or a CCD or CMOS device turns light into signal.
Both outlines cover these. If you test before March 1, 2027, also know CR: a photostimulable phosphor plate and a plate reader.
How do the histogram and exposure indicator work?
The histogram graphs how often each pixel value occurs. The system finds the values of interest (VOI), the part that holds diagnostic anatomy. Rescaling moves those values to a set place, and the look-up table (LUT) turns each input value into a display value. Picking the wrong anatomical menu applies the wrong reference.
Together these steps create the main digital trap. A wrong technique can still look right. AAPM Report 116 says overexposed images may not be dark and underexposed images may not look light. Exposure errors show up as noise changes instead. Over time this lets technique drift upward, which AAPM calls exposure creep.
So read the numbers:
- Exposure indicator: an estimate of the radiation that reached the receptor.
- Deviation index (DI): how far that exposure landed from the target. DI = 10 × log₁₀(indicated exposure ÷ target exposure).
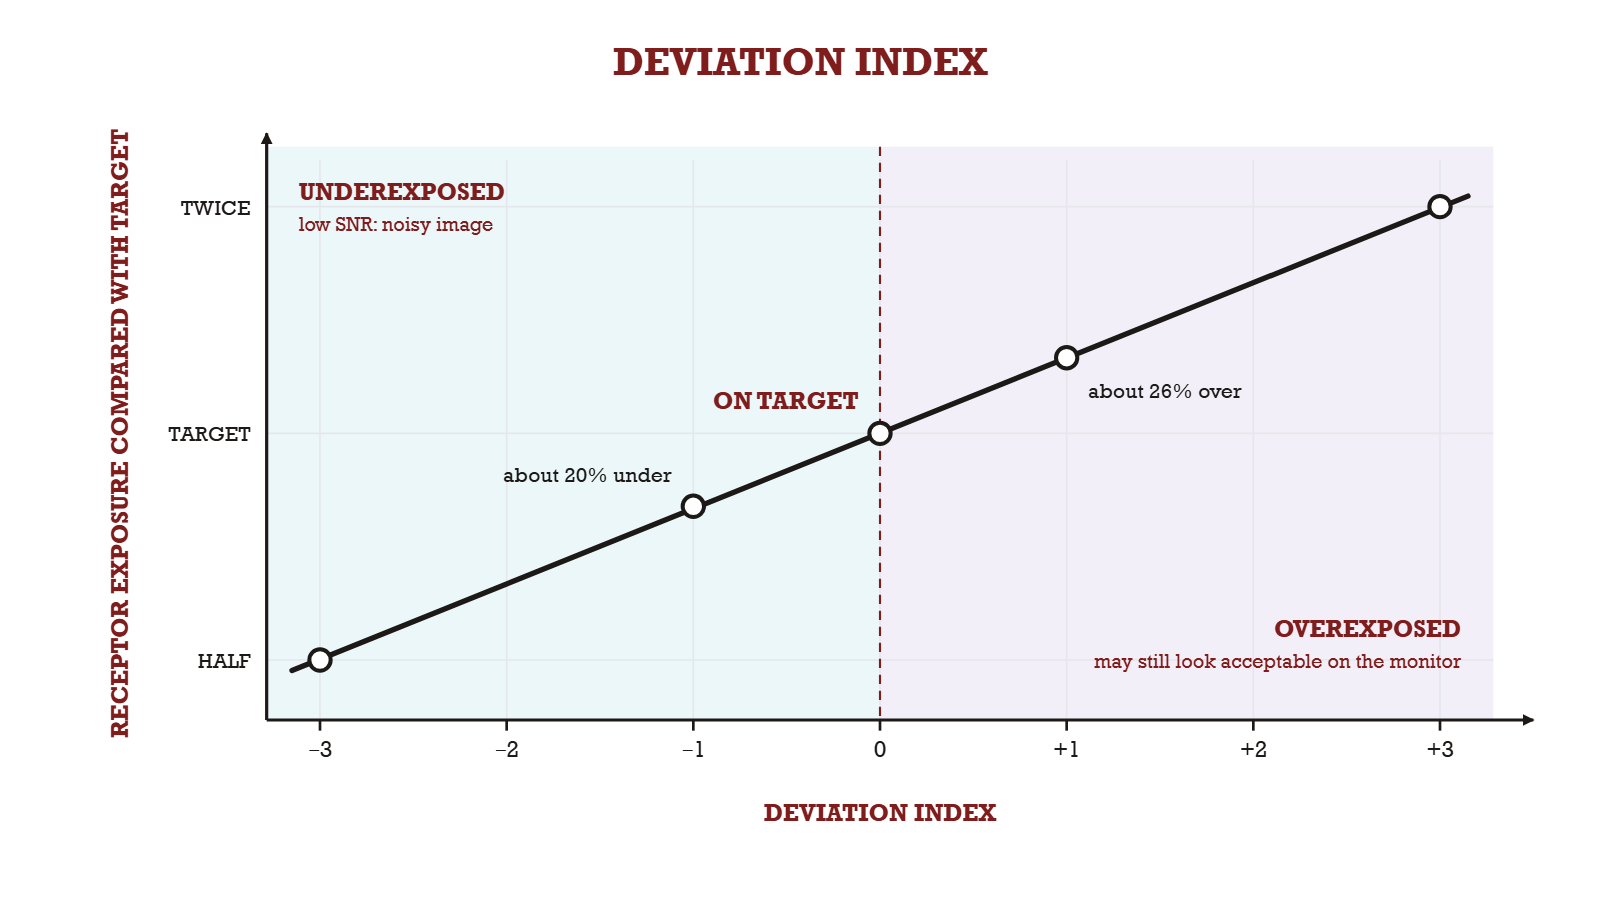
AAPM Report 116 suggests these control limits. Your department sets its own.
| DI | Meaning | Suggested action |
|---|---|---|
| Above +3 | Excessive exposure | Repeat only if anatomy is clipped. Management follow-up. |
| +1 to +3 | Overexposure | Repeat only if anatomy is clipped. |
| -0.5 to +0.5 | Target range | None |
| Below -1 | Underexposure | Consult a radiologist about a repeat |
| Below -3 | Severe underexposure | Repeat |
Bontrager describes DI as running from -3 to +3, but AAPM’s limits go past those ends, as above. DI can mislead. Poor collimation, a prosthesis or odd positioning can throw off the reading, so check the image for noise as well. Older vendor indicators differ too: Fujifilm’s S-number rises as exposure falls, while Agfa uses lgM and Kodak uses EI. That is why a standard index exists.
What do window width and window level do?
- Window width sets contrast. Narrow means short scale and high contrast. Wide means long scale and low contrast.
- Window level sets brightness. Which way it moves isn’t universal. Bontrager says the direction depends on the viewing software, with some PACS going darker and others brighter as level rises. Bushong gives no direction. Our window level direction page has the detail, so check your own system and what your program teaches.
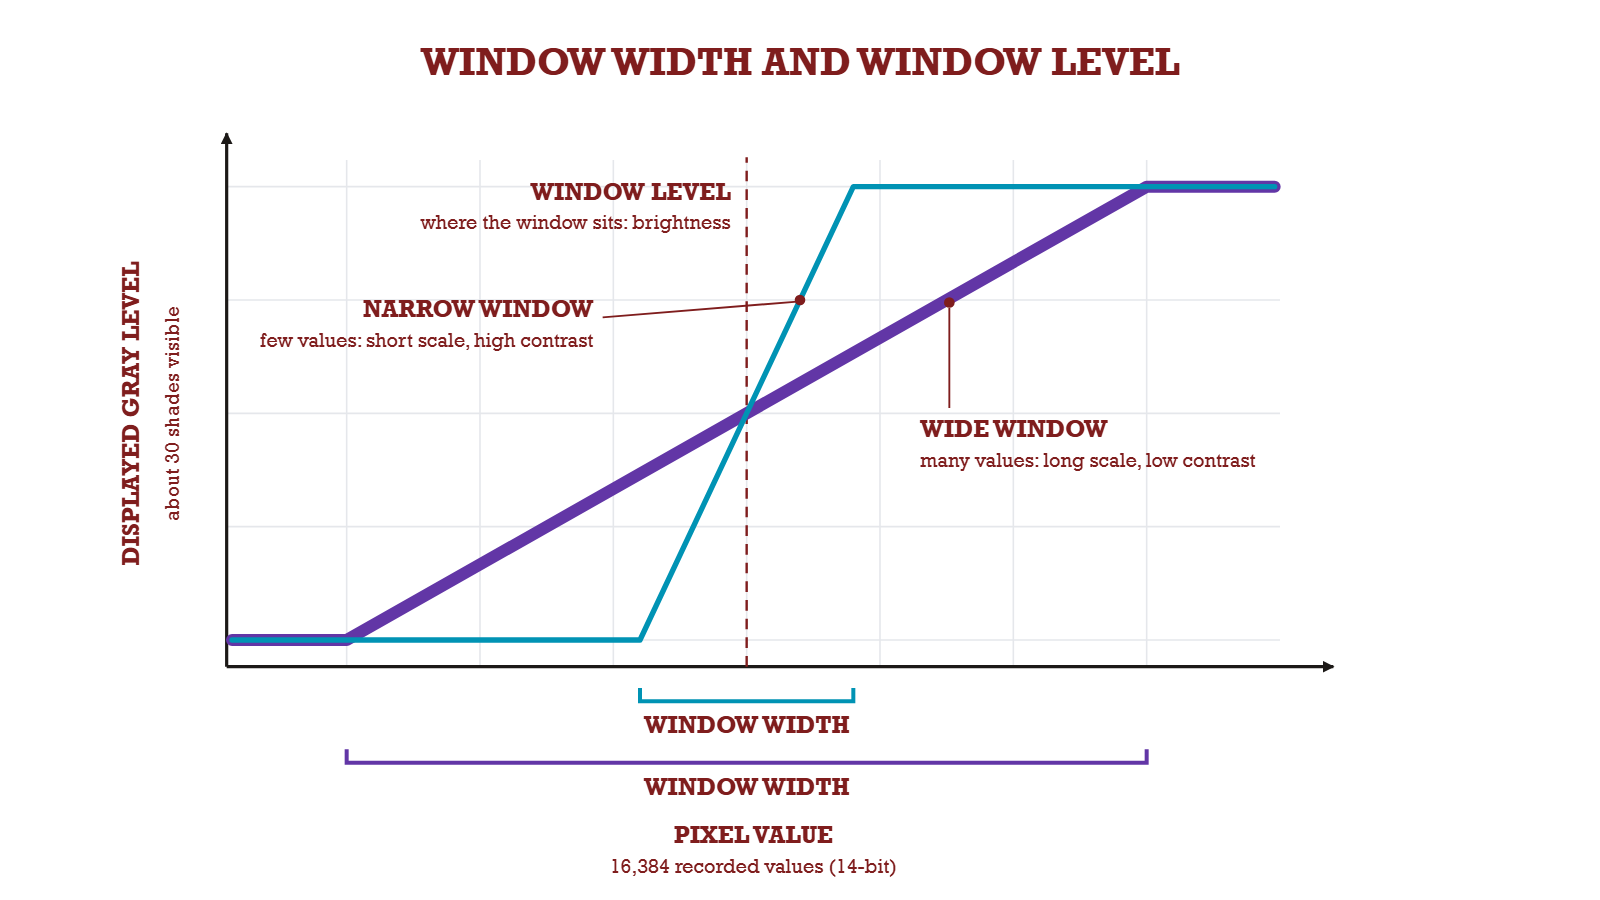
Why it matters: Bushong says a 14-bit detector can record 16,384 values, while most people can separate only about 30 shades. Window and level choose which range you see.
Windowing changes the display only. It doesn’t change the patient’s dose, and it can’t add information the exposure never recorded. AAPM Report 116 computes its standard exposure index and the DI from the for-processing pixel values, so windowing doesn’t move them. Older vendor indicators can differ: the same 2009 report notes that Fujifilm’s then-recent software let the user change the S-number afterward.
What QC numbers should you know?
Sources disagree here. Bushong’s QC table (2017) differs from current AAPM guidance. We lead with AAPM because it is the current official source, and you may meet the book figures in practice material, so read which framework a question uses.
| Test | Limit | Source |
|---|---|---|
| kVp accuracy | Within 5 kV or 5%, whichever is greater. Bushong’s table allows ±10%. | AAPM 150 |
| Timer accuracy | Within 1 ms at 20 ms or less. Within 5% above 20 ms. Bushong’s table: ±5% above 10 ms, ±20% at 10 ms or less. | AAPM 150 |
| Output reproducibility | Coefficient of variation no more than 0.05 | 21 CFR 1020.31(b) |
| Output linearity | Adjacent stations within 10% | AAPM 150 |
| HVL at 80 kVp | 2.9 mm Al (2.3 mm if made before June 10, 2006) | 21 CFR 1020.30 |
| Light field to x-ray field | Within 2% of SID | 21 CFR 1020.31(d) |
| AEC reproducibility | Coefficient of variation under 5% | AAPM 150 |
| Focal spot | Maximum size for each nominal size. Bushong’s table allows ±50%. | AAPM 150 |
A medical physicist does most of this annually, under AAPM Report 150. Bushong lists collimation checks twice a year and says to check aprons and gloves under fluoroscopy at least once a year, and your facility may check more often. Your part is to evaluate every image and to recognize and report malfunctions, which both outlines list. Follow your facility’s policy for a unit that fails.
The 2027 outline also lists display monitor QA, including the Grayscale Standard Display Function and luminance, plus viewing conditions such as viewing angle and ambient light.
For how exposure factors and filtration connect to dose, see our Radiation Protection guide.
What should you know about the x-ray tube?
The cathode holds the filament, in a focusing cup. Heat frees electrons by thermionic emission. Most tubes have a small and a large focal spot.
The anode is the target. A rotating anode spreads heat across a larger area. Over 99% of the electrons’ energy becomes heat rather than x-rays.
Heat units: HU = kVp × mA × s on single phase. Multiply by 1.4 for three-phase or high-frequency, the one factor Bushong gives for both. The older 1.35, 1.41 and 1.45 values aren’t in it. Example: 80 kVp, 200 mA and 0.5 s on a high-frequency unit is 80 × 200 × 0.5 × 1.4 = 11,200 HU.
How tubes fail: tungsten vaporizes off the filament until it thins and breaks. That tungsten also coats the enclosure, which can lead to arcing. Bearing wear and anode cracking from thermal stress are separate failures. So is a gassy tube, where the vacuum has failed.
How do you troubleshoot an image?
| What you see | Likely cause | First step |
|---|---|---|
| Noisy, low DI | Too few photons | More mAs, and check the DI limits |
| Looks fine, high DI | Overexposure hidden by processing | Lower technique next time |
| Clipped, burned-out anatomy | Detector saturation | Repeat is justified |
| Very dark, light or noisy, DI odd | Wrong menu or poor collimation | Check menu and margins |
| Blur | Motion, or large focal spot | Shorter time, immobilize, smaller spot |
| Magnified | Long OID or short SID | Reduce OID, raise SID |
| Foreshortened | Part angled to the receptor | Align part and receptor |
| Elongated | Tube or receptor angled | Align tube and receptor |
| Cutoff pattern | Grid error | Match the pattern to the error |
| Mark in the same place on every image | Receptor fault | Report it |
How should you study Image Production?
This order is our judgment:
- Radiographic Quality: the factor table, grids and technique charts.
- Equipment Operation and QA: tube, circuit, fluoroscopy and QC limits.
- Digital Image Processing: histogram, DI and windowing.
Then drill. The Image Acquisition set has 367 questions today and 326 from March 1, 2027. The Equipment QA set has 328 today and 311 from then. Every question has a written rationale. For how this section fits with the rest, see how to pass the ARRT registry.
To be clear about what’s free: the 3 free chapters are all Procedures (Skull, Elbow and Shoulder, Urinary), so no Image Production chapter is included. Sign up free for those chapters, 50 questions and 1 full 200-question timed mock, no card. Paid plans open soon: Monthly $39 that renews until you cancel, a 90-Day Pass at $99 once that never renews, or Annual at $199 a year (about $16.58 a month) that renews until you cancel.