Do grids reduce patient dose? No, a grid raises it, and it still earns its place on thick parts
Key takeaways
- Grids raise patient dose because technique goes up, usually several times over.
- Bushong's average factors: 5:1 = 2, 8:1 = 4, 12:1 = 5, 16:1 = 6. The true factor rises with kVp.
- Sherer and Bontrager use a grid for parts over about 10 cm, and Sherer adds techniques above 70 kVp. Some references say 13 cm.
- Grids are used for high-kVp chest work, and fluoroscopy units have them too, removable for children.
- Collimation lowers dose and reduces the scatter produced.
No. A grid raises patient dose. It’s still worth using on thick parts, because scatter would otherwise cut image contrast.
Why does a grid raise dose?
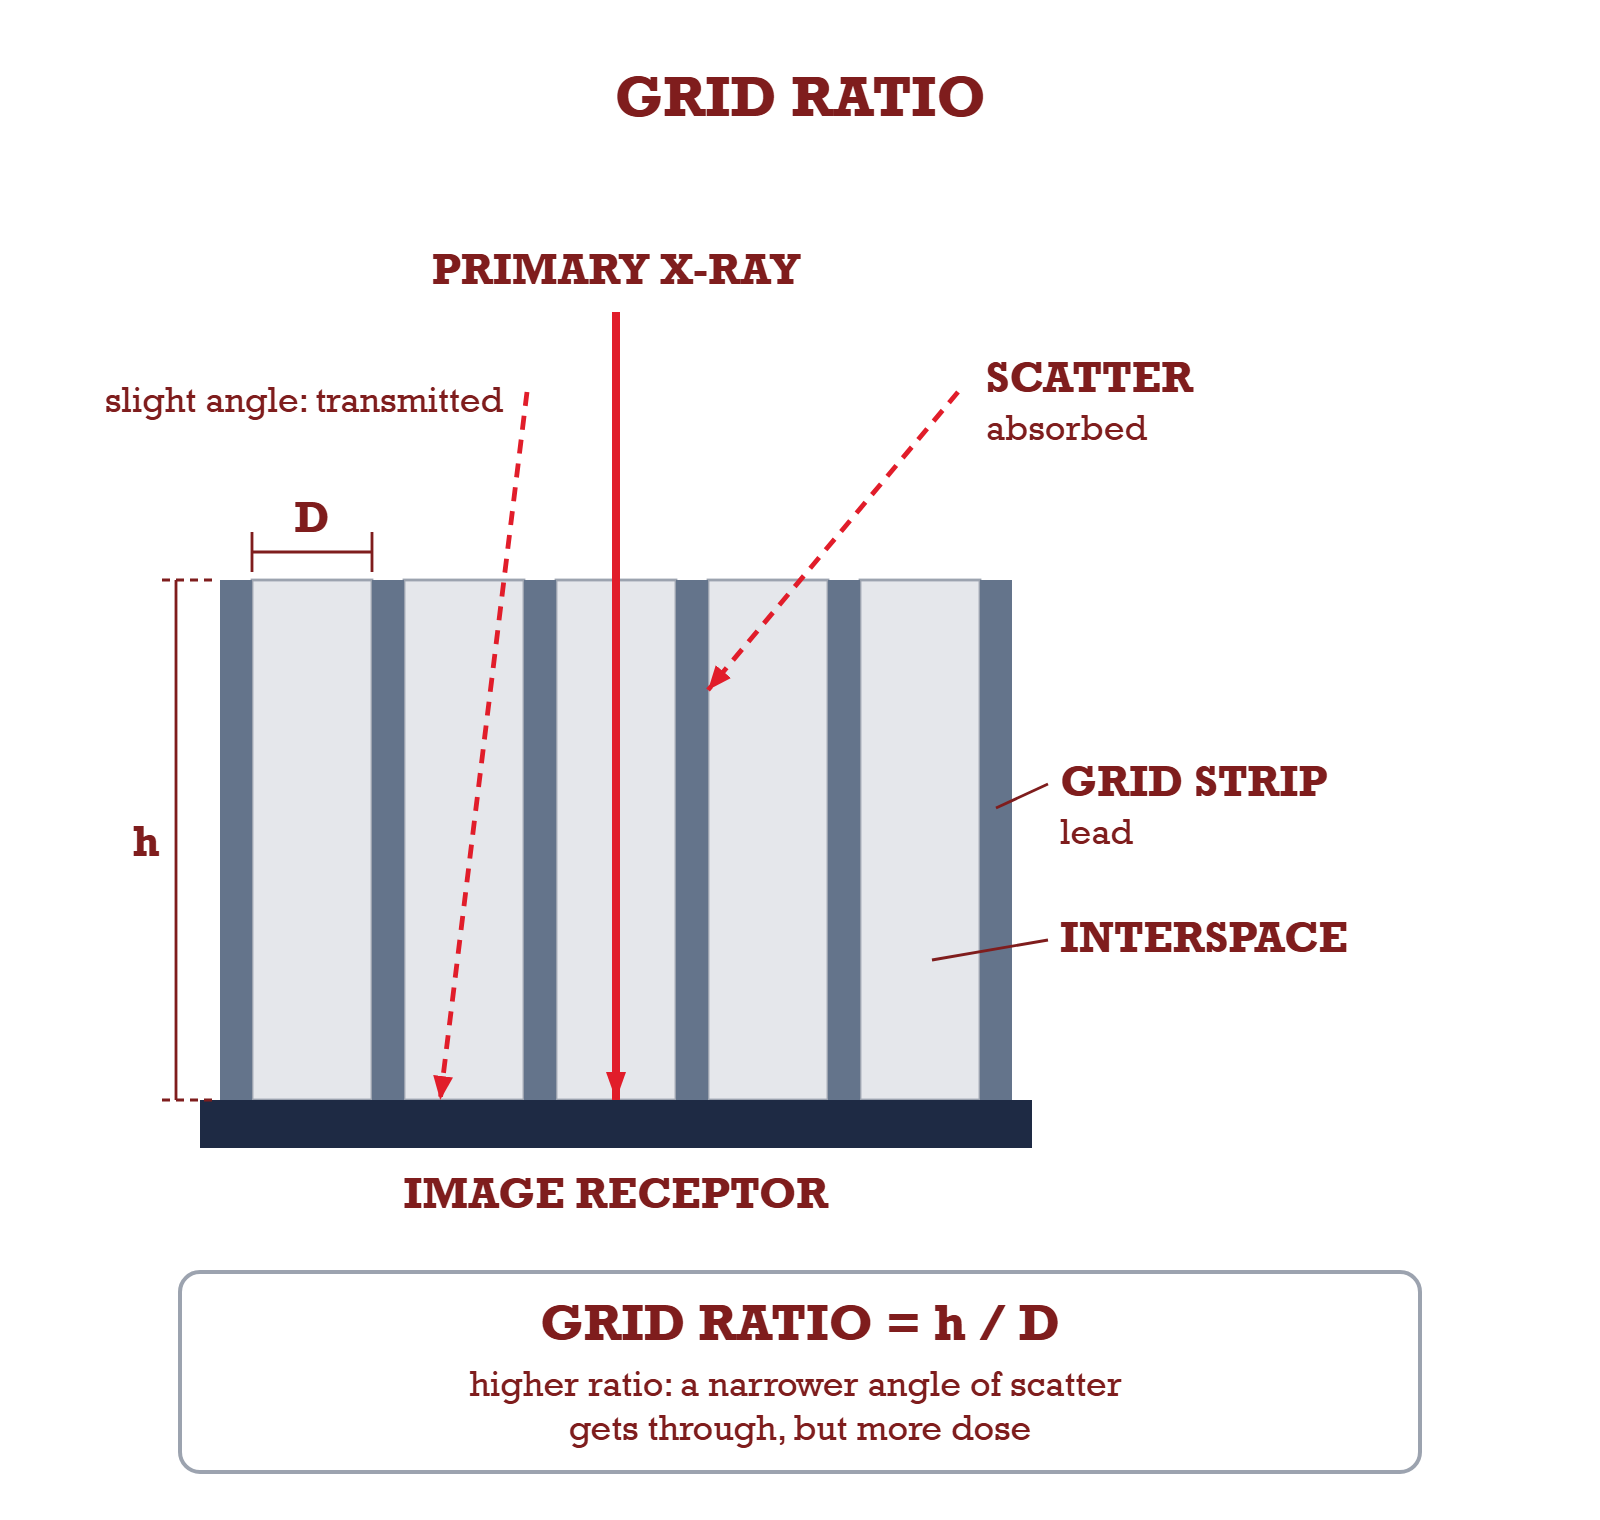
The grid sits between the patient and the receptor. It absorbs scatter after the beam leaves the patient, and it also stops some primary x-rays. Fewer x-rays reach the receptor, so you raise technique to get the same signal. The patient takes that extra exposure. Photons absorbed in the grid itself aren’t patient dose. The higher technique is what costs dose.
How much does it raise dose?
The Bucky factor tells you. Bushong defines it as patient dose with a grid divided by patient dose without one.
| Grid ratio | 70 kVp | 90 kVp | 120 kVp | Average |
|---|---|---|---|---|
| No grid | 1 | 1 | 1 | 1 |
| 5:1 | 2 | 2.5 | 3 | 2 |
| 8:1 | 3 | 3.5 | 4 | 4 |
| 12:1 | 3.5 | 4 | 5 | 5 |
| 16:1 | 4 | 5 | 6 | 6 |
The average column is Bushong’s, and it matches our Image Production guide. Example: 10 mAs with no grid becomes 40 mAs on an 8:1 grid. To convert, use new mAs = old mAs x (new factor ÷ old factor). The formula pages include grid conversion among the 5 free ones.
Bushong says going from 12:1 to 16:1 adds little scatter cleanup for a large dose increase, so 16:1 is uncommon and 8:1 is a common compromise. Bushong also says that, in general, high kVp with a high-ratio grid gives lower dose than low kVp with a low-ratio grid, at equal image quality. Its own dose table is mixed: 8:1 at 110 kVp is below 5:1 at 70 kVp, while 16:1 at 110 kVp is above it. See kVp vs mAs for why.
When do you use a grid, and when not?
- Parts over about 10 cm: use a grid. Sherer and Bontrager both give about this rule. Sherer words it two ways: 10 cm or greater on one page, and more than 10 cm or techniques above 70 kVp on another. Bontrager notes some references say 13 cm, so the average knee can go either way.
- Parts about 10 cm or less: usually no grid, such as small extremities and many small children.
- High kV chest: Bontrager says over 100 kV requires a grid as a general rule. An earlier version of this page said a grid was redundant here. That was wrong.
- Mobile chest: Bontrager says a low-power unit limited to 90 kV may allow no grid, but doesn’t recommend it. Stationary grids work on mobile exams with careful centering, because misalignment causes cutoff and a repeat.
- Fluoroscopy: grids are on ARRT®‘s outline here too. Bontrager says they at least double dose, that removing one for a child lowers dose with little image loss, and that units should allow easy removal.
What about virtual grids and collimation?
The 2027 outline adds virtual grids. It doesn’t define them, and Bushong, Bontrager, Merrill’s and AAPM Report 150 don’t use the term. The ACR-AAPM practice parameter mentions “software-based scatter corrections” as an option beside grids, without calling them virtual grids. So we won’t claim a dose figure for them.
Collimation is the tool that helps both ways. It reduces the scatter produced, and it limits the tissue you irradiate. The Radiographic Quality chapter and the Image Acquisition practice set cover both.
Frequently asked questions
Do grids reduce patient dose?
No. Grids improve contrast by absorbing scatter, but technique must increase to keep the same receptor signal, so patient dose goes up. Bushong defines the Bucky factor as patient dose with a grid divided by patient dose without one.
What is the Bucky factor?
It's the amount technique must rise when you add a grid. Bushong's average values are 5:1 = 2, 8:1 = 4, 12:1 = 5 and 16:1 = 6, and the factor rises with kVp.
When should you not use a grid?
Bontrager's general rule is a grid above 10 cm, so parts about 10 cm thick or less often go without one, such as small extremities and many small children. Sherer also calls for a grid on techniques above 70 kVp. Bontrager also says grids should be used with discretion in pediatric fluoroscopy.
Are grids used in fluoroscopy and on chest x-rays?
Yes. Bontrager says high kV chest work requires a grid as a general rule, and that fluoroscopy grids should be easy to remove for children. ARRT's outline lists grids under fluoroscopy.
Sources
Found an error? Email [email protected] with the page and the source.
- ACR-AAPM-SIIM-SPR Practice Parameter for Digital Radiography, revised 2022, amended 2023, PDF p.6 Guidance
- ARRT Radiography Examination Content Specifications, effective March 1, 2027 (repo copy) Official
Know the answer. Now drill it.
Free tier includes 3 chapters, 50 practice questions and 1 full timed mock. No credit card.