Radiation Protection on the ARRT® Radiography exam splits into two parts: keeping patient dose down, and keeping your own dose down. The registry tests both, and it uses SI units as its primary units. This guide says which numbers come from a federal rule, which come from NCRP by way of the textbooks listed under sources, and where the books disagree.
This page is a study reference, not clinical guidance. Follow your state rules, your facility’s radiation safety program and your training.
How many Radiation Protection questions are on the ARRT exam?
Radiation Protection has 29 of 200 scored questions through February 28, 2027, and 25 from March 1, 2027. That is a drop from 14.5% to 12.5%. It sits in the Safety section, which falls from 50 to 46. The other Safety category, Radiation Physics and Radiobiology, stays at 21.
ARRT doesn’t publish how many questions cover each topic, so we won’t guess at a split. Not sure which section is weakest? Try the free practice test. For the whole exam plan, read how to pass the ARRT Radiography exam.
Does ALARA apply to patients or only to personnel?
ALARA means as low as reasonably achievable. In ARRT’s outlines, it applies to personnel. Both the 2022 and 2027 outlines list “Personnel Protection (ALARA)” and carry a note dated August 24, 2016. It says “the ALARA concept is specific to personnel protection and is listed only for that section.”
The same note says radiographers must still apply protection principles to minimize bioeffects for both patients and personnel. Patient dose is simply filed under a different heading, “Minimizing Patient Exposure”.
You will see the term used more widely elsewhere:
- The NRC’s rule, 10 CFR 20.1101, uses ALARA for occupational doses and doses to members of the public.
- AAPM’s shielding statement describes patient shielding as long considered “consistent with the ALARA principle”.
- Ehrlich and Coakes’s patient care textbook applies ALARA to both patients and workers.
So on the exam, tie the word ALARA to your own protection, and treat patient dose reduction as its own topic. The right action rarely changes. Only the label does. That is our reading of the note, not an ARRT statement about how a question is scored.
What are time, distance and shielding?
These are the three basic methods of personnel protection in the outline.
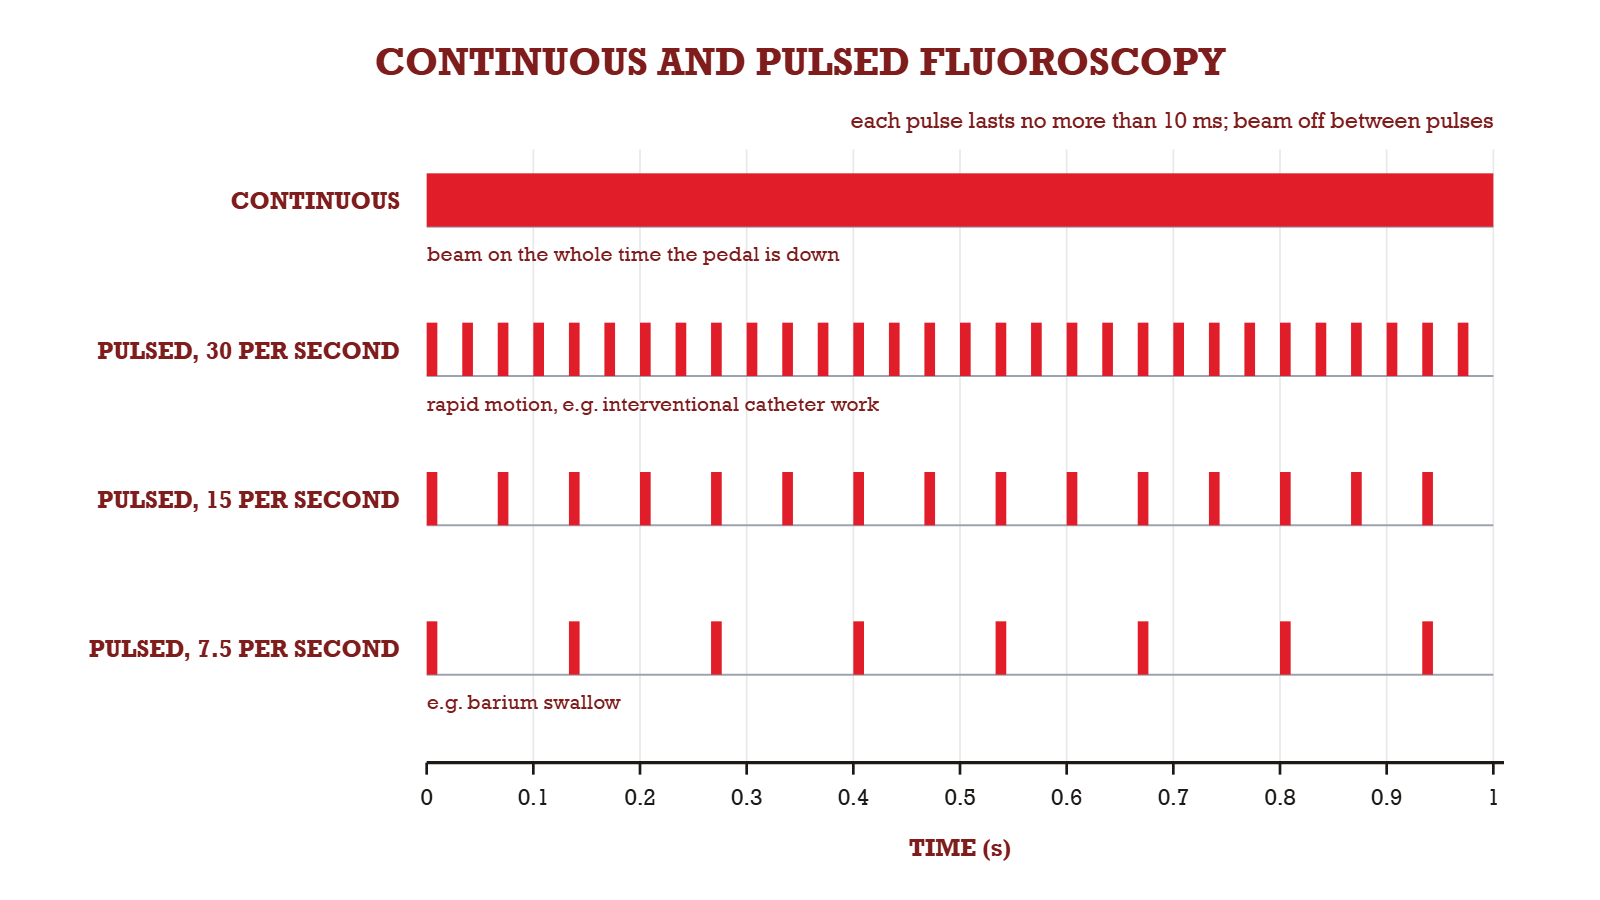
Time. Less beam-on time means less dose. In fluoroscopy, that means short pedal taps, pulsed mode and last-image hold.
Distance. Intensity falls with the square of the distance from the source. Double your distance and intensity drops to one-fourth. Going from 2 m to 4 m cuts it to one-fourth, and going to 6 m cuts it to one-ninth. Sherer puts scatter at 1 m, at 90 degrees to the beam, at about 1/1000 of the primary beam.
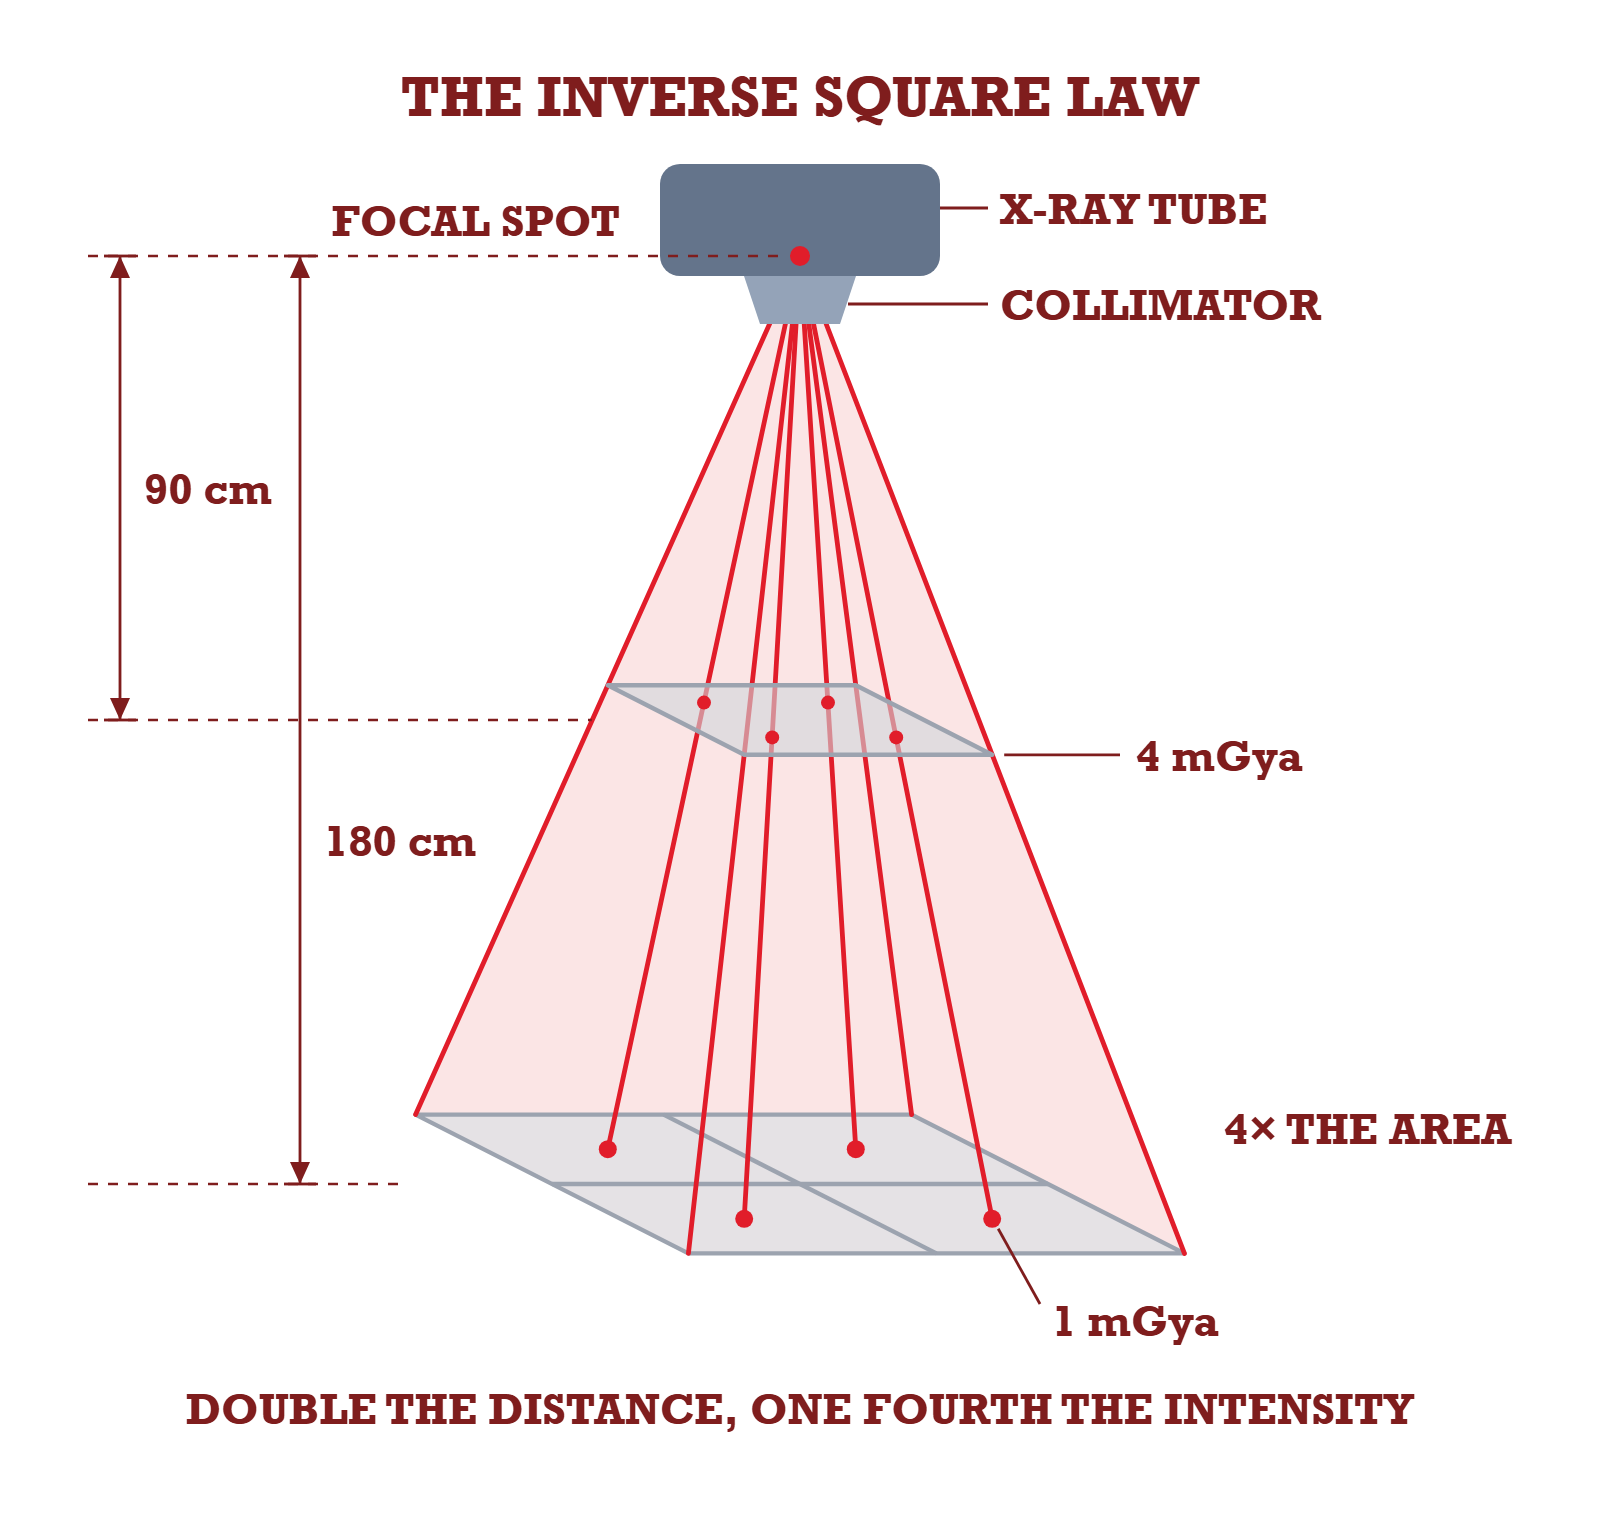
Shielding. Put attenuating material between you and the source. The 2027 outline adds the words “need and appropriate use” here. Lead is the usual material, and barriers count too.
Your main source of dose is scatter from the patient, so the patient is a source in the outline’s own list. Bushong says radiology staff should never hold patients. Use a mechanical device first. If someone must hold, Sherer and Bontrager say to use a person who isn’t a radiation worker, in protective apparel and never pregnant. Bontrager also rules out anyone under 18.
What are the dose limits for radiographers?
These are the numbers and where each one comes from. “NRC rule” means we read it in 10 CFR Part 20. “NCRP” means Sherer and Bushong report it from NCRP Report 116. We read those books, not the report itself.
| Who or what | Limit |
|---|---|
| Occupational, whole body (effective dose) | 50 mSv a year |
| Occupational, skin or extremity | 500 mSv a year |
| Occupational, lens of the eye (NRC rule) | 150 mSv a year |
| Embryo-fetus, declared pregnancy | 5 mSv for the entire pregnancy |
| Member of the public | 1 mSv a year |
NRC limits from 10 CFR 20, not ARRT limits. NCRP recommends a lower lens limit. See the lens section.
| Who or what | Limit | Basis |
|---|---|---|
| Occupational, whole body | 50 mSv (5 rem) a year, effective dose | NRC rule, 20.1201 |
| Occupational, skin or extremity | 500 mSv (50 rem) a year | NRC rule, 20.1201 |
| Occupational, lens of the eye | 150 mSv (15 rem) a year | NRC rule, 20.1201. See the next section. |
| Member of the public | 1 mSv (0.1 rem) a year | NRC rule, 20.1301 |
| Embryo-fetus, declared pregnancy | 5 mSv (0.5 rem) for the entire pregnancy | NRC rule, 20.1208 |
| Embryo-fetus, per month | 0.5 mSv (0.05 rem) | NCRP. The NRC rule instead says to avoid substantial variation above a uniform monthly rate. |
| Occupational, cumulative | 10 mSv × age in years | NCRP. Not in the NRC rule. |
| Under 18, occupational | 5 mSv (0.5 rem) a year, 10% of the adult limit | NRC rule, 20.1207 |
| Under 18, education and training | 1 mSv (0.1 rem) a year | NCRP |
Four things to remember:
- The NRC writes Part 20 for its licensees. State and facility rules decide what binds you at work.
- The ARRT outline cites NCRP for these topics, and NCRP limits and NRC limits aren’t always the same. Bushong and Sherer treat 0.5 mSv a month as a limit, and the NRC rule doesn’t.
- These limits don’t apply to patients. The public limit in 20.1301 excludes doses from your own medical care.
- Watch for one book conflict. Ehrlich and Coakes prints 50 mSv for the pregnant worker over 9 months. The NRC rule, Sherer, Bushong and Bontrager all say 5 mSv, so use 5 mSv.
What is the dose limit for the lens of the eye?
This is the one number that is moving, so here is exactly what we could and couldn’t check.
Confirmed:
- The NRC limit is 150 mSv (15 rem) a year, in 10 CFR 20.1201(a)(2)(i).
- NCRP Commentary 26 (2016) recommended lowering NCRP’s limit from an equivalent dose of 150 mSv to an absorbed dose of 50 mGy a year. We read this in the abstract of the published overview, not in the commentary itself. Note the unit: mGy, not mSv.
- ICRP recommends 20 mSv a year averaged over 5 years, with no single year above 50 mSv.
- The 2022 ARRT outline cites NCRP Report 116 for personnel monitoring. The 2027 outline cites NCRP Report 180, plus 21 CFR. We haven’t read that report and give no value from it.
- Sherer (2018) and Bushong (2017) both print 150 mSv from NCRP Report 116. Neither mentions Commentary 26 or Report 180, so don’t treat them as current on this one number.
Not confirmed:
- Which value ARRT’s items use. ARRT doesn’t publish that.
Our advice, marked as judgment: through February 28, 2027, know 150 mSv. For an exam on or after March 1, 2027, know both numbers and read the stem. If it names the NRC or 10 CFR, the answer is 150 mSv. If it asks for the current NCRP recommendation, the latest value we could confirm is 50 mGy. Ask your program director what your program teaches.
Either way, protect your eyes. The NRC paper notes that lens dose can be well above effective dose when an apron shields the trunk, and that leaded glasses should have side shields.
What lead equivalent do protective devices need?
ARRT’s outline cites NCRP Report 102 for minimum lead equivalents. We read a public copy: it says at least 0.5 mm for aprons worn in the fluoroscopy room. It also says a fluoroscopist’s hand shall not be placed in the useful beam unless the beam is attenuated by the patient and a protective glove of at least 0.25 mm, so a glove alone doesn’t make it acceptable. The table’s values come from Sherer. Bushong agrees on the apron minimum, the curtain and the slot cover.
| Device | Lead equivalent |
|---|---|
| Apron, minimum | 0.25 mm Pb |
| Apron, fluoroscopy and interventional | 0.5 mm Pb |
| Thyroid shield | 0.5 mm Pb |
| Lead glasses | 0.35 mm Pb |
| Lead gloves | 0.25 mm Pb |
| Fluoroscopy curtain or sliding panel | At least 0.25 mm Pb |
| Bucky slot cover | At least 0.25 mm Pb |
On fluoroscopy, Sherer calls 0.5 mm the minimum, NCRP Report 102 also says at least 0.5 mm, and Bushong says at least 0.25 mm is required and 0.5 mm is normal. 21 CFR 1020 doesn’t mention aprons. The Health Physics Society says state regulations set the minimums, commonly 0.25 mm in some states and 0.5 mm in others. We didn’t open any state regulation, so ask your radiation safety officer what applies. See lead apron attenuation for the percentages, and whether a thyroid shield is required for what the rules say.
Check aprons and gloves for cracks at least once a year, by fluoroscopy or by high-kVp radiography. Bushong and Sherer both give this interval. Sherer calls it a regulatory requirement but names no regulation, and we didn’t find one. Hang aprons on a rack, since folding can crack them. If a check finds cracks, tears or holes, Bushong says the apparel may require replacement.
Where do you wear a dosimeter?
Types named in the 2027 outline are TLD, OSL and DIS. A dosimeter measures dose. It doesn’t protect you.
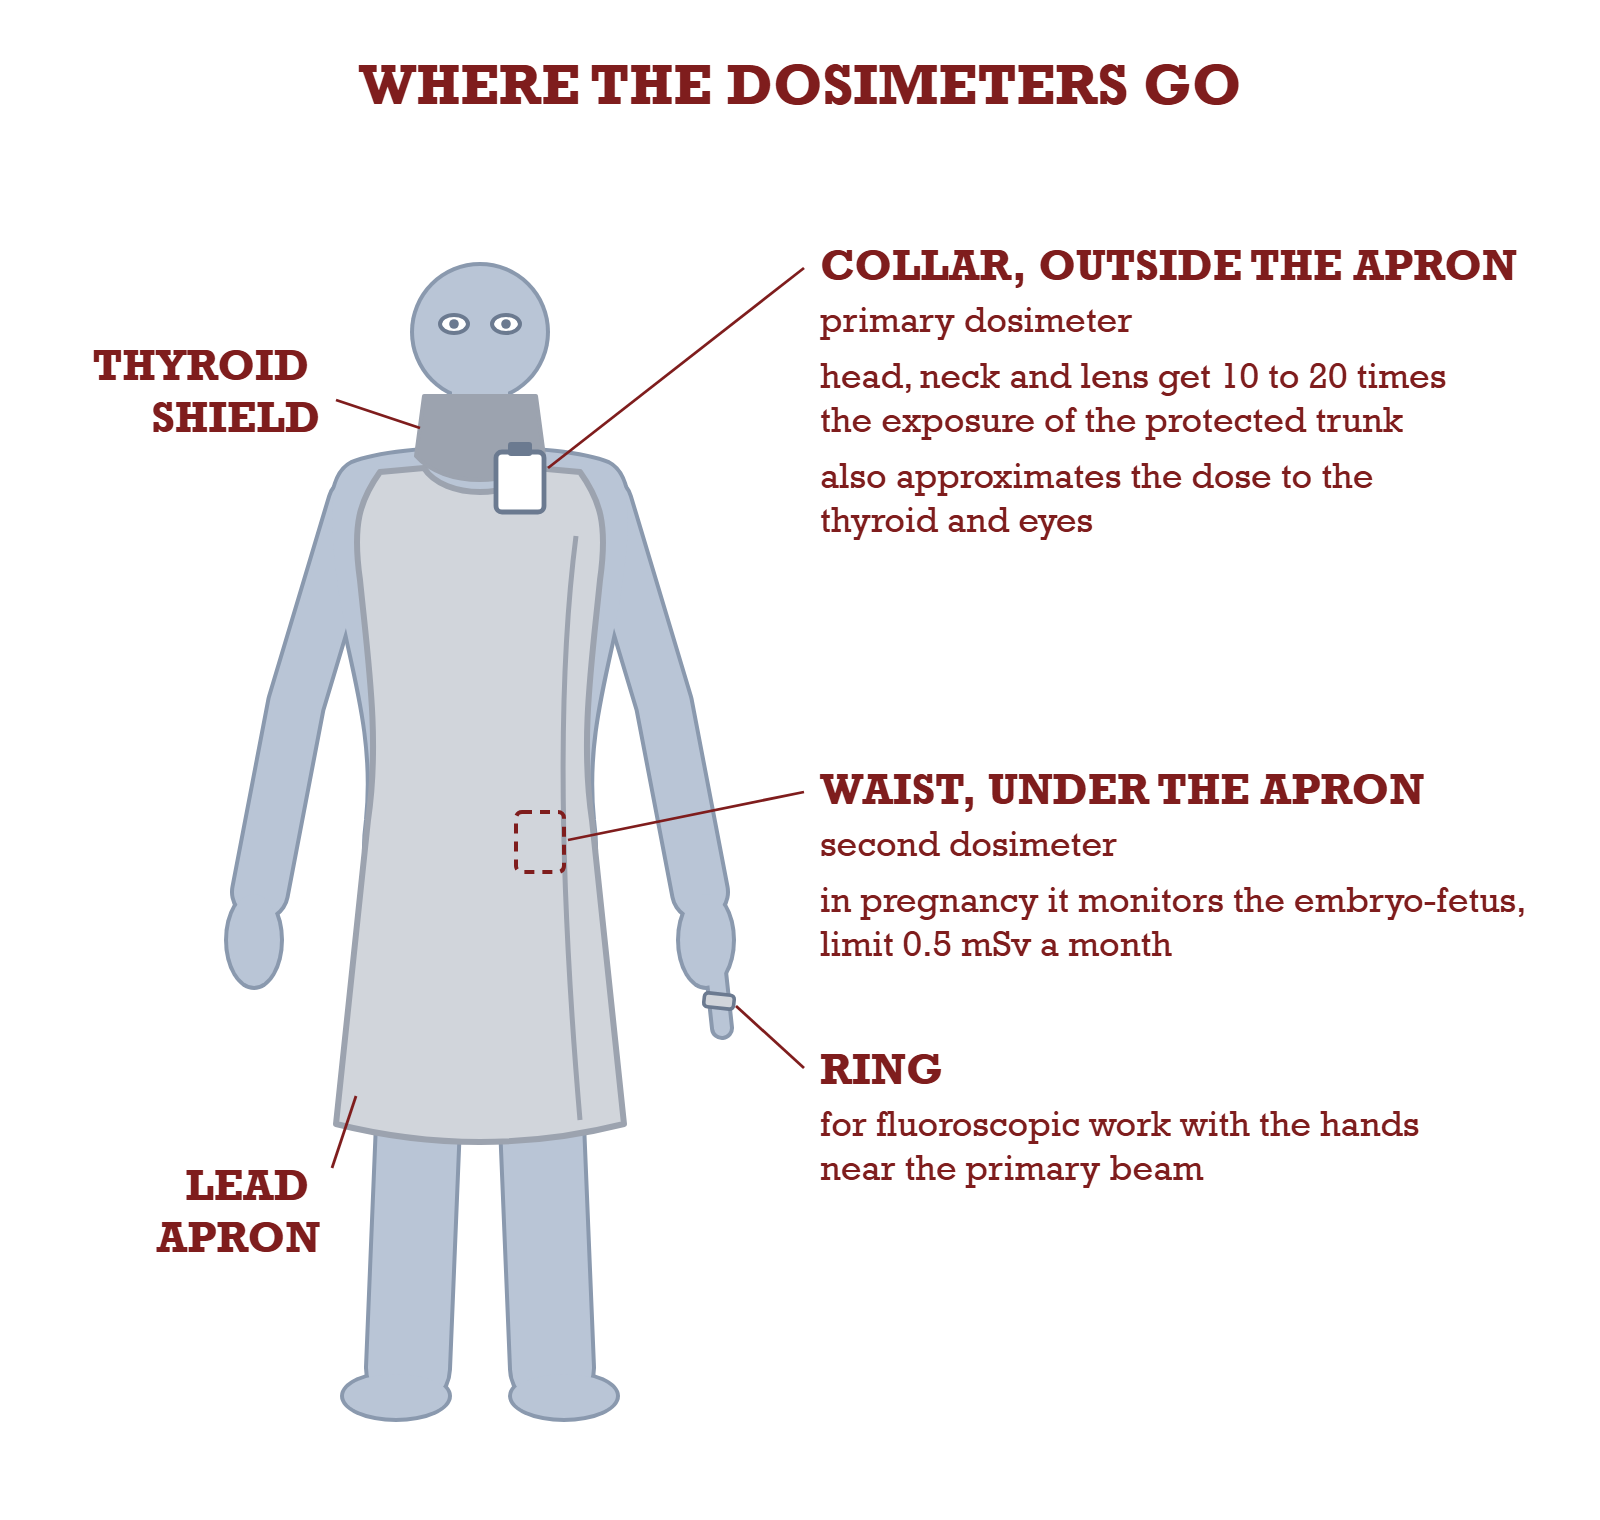
- With an apron: at the collar, outside the apron. All the books we read agree. Under the apron, it would read falsely low and hide the dose to your head and eyes.
- Without an apron, in routine radiography: the books disagree. Sherer and Ehrlich and Coakes say collar level. Bushong and Bontrager accept the front of the body at waist or chest level, as our chapter does. Your program or radiation safety officer decides at work. Our judgment: the collar works in both settings, and Sherer stresses wearing the badge in the same place every time.
- Second badge in long interventional work: some facilities add one at the waist, under a wraparound apron. See the two-badge formula.
- Declared pregnancy: a second dosimeter at the waist, under the apron, with its record kept separately.
- Who must be monitored: the NRC rule requires it for adults likely to get more than 10% of the limits, and for declared pregnant workers likely to get more than 1 mSv (0.1 rem) during the pregnancy.
Declaring a pregnancy is voluntary and must be in writing. The NRC limit then protects the embryo-fetus, and the worker’s own limit is unchanged. We found no rule that bars pregnant staff from the room. Sherer and Bontrager say a pregnant radiographer can keep working in fluoroscopy under normal safety practice, so the facility’s program decides any work changes.
How do you reduce dose in fluoroscopy?
Bushong says at least 95% of a radiographer’s occupational dose comes from fluoroscopy and mobile radiography. For patients, the picture differs: CT was about 62% of collective patient dose in the U.S. in 2016 (444,000 of 717,000 person-Sv, from NCRP Report 184 data).
These are the fluoroscopy facts tied to federal rules, in 21 CFR 1020:
- Source-to-skin distance: at least 38 cm on stationary units and at least 30 cm on mobile units.
- Beam-on signal: an audible signal at 5 minutes of irradiation time. It’s a prompt, not a dose limit.
- Air kerma rate: generally no more than 88 mGy per minute, or 176 mGy per minute with high-level control active, at the measurement point.
- Last-image hold: required on units made on or after June 10, 2006.
These working habits come from Sherer and Bushong:
- Use pulsed mode at the lowest rate that gives a usable image, and keep beam-on time in short taps.
- Use last-image hold to study a frame instead of exposing again.
- Know what high-level control costs. Sherer says the exposure rate in this boost mode may significantly exceed the routine fluoroscopy rate.
- Use magnification only when asked. On an image intensifier it raises mA and patient dose. On a digital system a zoom may not change exposure, so the physicist or manufacturer has to tell you.
- Keep the curtain and Bucky slot cover in place.
- Step back when you can, or stand behind the radiologist or in the booth. If your back could face the source, Sherer says a wraparound apron protects best.
On a C-arm:
- Put the tube under the patient. With the tube on top, scatter and staff exposure rise.
- Keep the image intensifier as close to the patient as you can.
- For a cross-table shot, stand on the image intensifier side. Sherer says scatter on the tube side is typically 2 to 3 times higher.
- Wear a 0.5 mm apron and a thyroid shield, and use the cable’s full length to gain distance.
The 2027 outline splits the fluoroscopy positioning item into patient positioning and varying the beam angle, and groups cumulative air kerma, dose rate display and time documentation as dose monitoring equipment.
Where do you stand for a mobile exam?
Stand at least 2 m from the patient, the tube and the useful beam, and wear an apron. That is Sherer’s wording, and Bushong gives 2 m from the tube. Merrill’s writes 6 feet (2 m). Strictly, 6 feet is about 1.8 m. ARRT uses SI as its primary units, so learn 2 m first. We found no such distance in 21 CFR 1020. NCRP Report 102 says the operator shall stand at least 2 m (6 ft) from the patient, the x-ray tube and the useful beam, so this is an NCRP recommendation, not a federal rule.
Where you can, also stand at a right angle to the line between the beam and the patient, where scatter is lowest. Sherer says to deal with distance and shielding first.
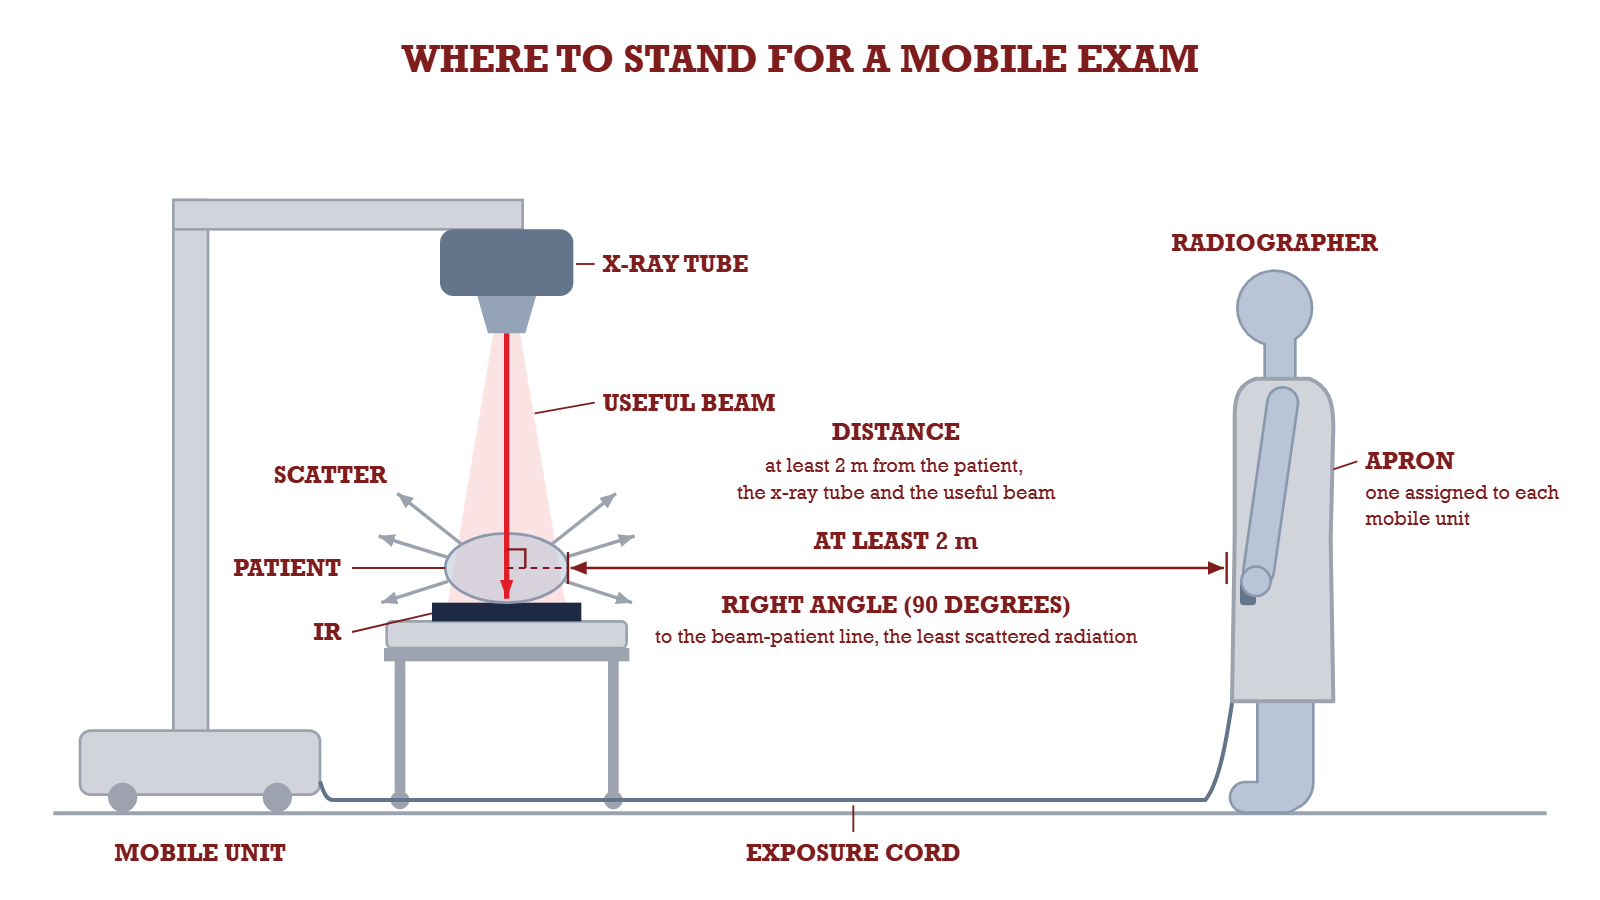
Bontrager says only people needed for the exam should stay in the room, and anyone who stays gets protective apparel. Each mobile unit should have its own apron, as Sherer and Bushong both say.
How do you minimize patient exposure?
Good technique does the heavy lifting. Both outlines list these under the patient heading:
- Exposure factors: kVp, mAs and AEC.
- Beam restriction: collimate to the area of interest. Tighter than the receptor is allowed and often better.
- Filtration, grids and the image receptor.
- Patient considerations: positioning and clear communication prevent repeats. See the most common cause of repeat exposures. The 2027 list adds pregnancy and swaps “morbid obesity” for “body habitus”.
- Dose documentation and the DAP meter.
- Pediatric care: Image Wisely and Image Gently are named as resources in the 2027 outline.
A possibly pregnant patient. Ask before you expose, and ask the date of the last menstrual period. Tell the radiologist if the answer is yes or unsure. Sherer strongly recommends a pregnancy test before substantial pelvic exposure if there’s doubt. Then follow your facility’s protocol.
The two timing rules are worth knowing by name, and the sources don’t agree on them:
- 10-day rule: schedule pelvic and lower abdominal exams in the first 10 days after menstruation starts. Ehrlich and Coakes says pregnancy is least likely then. Bontrager calls the rule obsolete, because canceling a needed exam can do more harm than the fetal dose. Merrill’s still uses it for bone densitometry. Sherer reports both NCRP advice to book nonurgent abdominal exams in the first few days after menses and an ACR position that they need not be postponed.
- 28-day rule: none of those five books states it. The UK’s Royal College of Radiologists describes it this way: if a period is overdue and the patient can’t be sure she isn’t pregnant, consider postponing, usually after talking to the radiologist. The same 2013 guidance suggests limited use of the 10-day rule for high-dose exams such as barium enema and abdominal or pelvic CT. That is UK guidance, not a U.S. rule.
Bontrager adds a useful sorting rule: above the diaphragm or below the hips, scattered fetal dose is very low and the exam may proceed normally.
AAPM CARES quotes the American College of Obstetricians and Gynecologists: “With few exceptions, radiation exposure through radiography, computed tomography scan, or nuclear medicine imaging techniques is at a dose much lower than the exposure associated with fetal harm.”
Are gonadal and fetal shields still used?
Routine use is ending, but the answer depends on who you ask and where you work. Sherer (2018), Bushong (2017) and Ehrlich and Coakes (2021) all still teach shielding, and Ehrlich and Coakes calls it required in some cases. The statements below are newer or carry more authority, so go with them over the books:
- April 2019, AAPM: routine patient gonadal and fetal shielding should be discontinued. Shields can obscure anatomy and interfere with AEC, and any benefit is minimal to nonexistent.
- January 12, 2021, NCRP Statement 13: routine gonadal shielding isn’t justified in abdominal and pelvic radiography. NCRP’s companion document notes that some state rules still require it.
- January 2021, ASRT: it’s appropriate to stop shielding for abdominal and pelvic imaging. ASRT still supports shields where placement is appropriate, such as a lap shield for an extremity exam.
- Spring 2021, ARRT: institutions may adopt these recommendations to varying degrees, and programs should still teach shielding. ARRT’s exams may not refer specifically to gonadal and fetal shielding procedures, but they will cover patient radiation exposure and protection.
- February 21, 2023, FDA: the gonad shielding recommendations in 21 CFR 1000.50 were removed.
Patient shielding isn’t listed under “Minimizing Patient Exposure” in either outline. ARRT also says it avoids content where resources conflict. So learn why routine shielding ended, know that the older technique exists, and follow state rules and facility protocol at work.
If a patient insists on a shield, AAPM CARES says it’s at the technologist’s discretion, as long as image quality isn’t compromised and overall dose isn’t increased.
What do dose-reduction scenarios look like?
Practice with scenarios like these. They are our examples, not ARRT items.
| Scenario | Commonly taught action |
|---|---|
| The field is open wider than the anatomy of interest | Collimate to the area of interest |
| A patient may be pregnant and has an abdomen series ordered | Stop and tell the radiologist. Follow protocol. |
| You’re close to the patient on a mobile exam | Step back to at least 2 m, at a right angle, with your apron on |
| A child is booked at an adult technique | Use a pediatric technique and collimate tightly |
What units does the exam use?
ARRT says SI units are the primary units on the exam. The 2027 outline cites NCRP Report 184 for them, where the 2022 outline cited Report 160.
| Quantity | SI unit | Older unit | Conversion |
|---|---|---|---|
| Absorbed dose | Gray (Gy) | rad | 1 Gy = 100 rad |
| Dose equivalent and effective dose | Sievert (Sv) | rem | 1 Sv = 100 rem |
| Exposure | C/kg | Roentgen (R) | SI unit has no special name |
| Air kerma | Gray (Gy) | Dose area product is air kerma times area |
For x-rays, the NRC quality factor is 1, so 1 Gy of x-rays equals 1 Sv. For alpha particles it’s 20, and for neutrons of unknown energy it’s 10. Effective dose sums dose across tissues, weighted by each tissue’s sensitivity, and it’s used to compare risk across exams. Our formula toolkit has the dose conversions, which are part of a paid plan.
What else changes in this section on March 1, 2027?
Besides the question count and the items above:
- The patient heading becomes “Minimizing Patient Exposure and Repeats”.
- “Image receptors” becomes “digital detector”, with DQE and exposure latitude as examples.
- Personnel monitoring now reads “recommendations and regulations”, citing NCRP Report 180 and 21 CFR.
The 2027 changes page covers the rest of the exam. For the digital side, including CR leaving the outline, read our Image Production guide.
How should you study Radiation Protection?
Learn the science first, then the rules. Read the Radiation Physics and Radiobiology chapter, then the Radiation Protection chapter. Then drill the Radiation Protection practice set, which has 317 questions today and from March 1, 2027. Every question has a written rationale. Infection control and contrast reactions sit in the sister guide, ARRT Patient Care.
The free tier is 3 chapters (Skull, Elbow and Shoulder, Urinary), 50 questions and a timed 200-question mock, with no card. Those are Procedures chapters, so no Safety chapter is free. You can still sign up free and use the mock to find your gaps. The two Safety chapters come with a paid plan: $39 a month, which renews until you cancel, $99 for a 90-day pass with no renewal, or $199 a year (about $16.58 a month), which renews yearly until you cancel. Paid plans open soon.